Pelvic obliquity as a factor in dysplastic hip in infancy
Related Experiment Video
Updated: Jan 19, 2026
Author Spotlight: A Novel 3D-Printed Titanium Implant for Minimally Invasive Treatment of Hip Dysplasia in Young Dogs
Published on: April 19, 2024

Insights
Pelvic obliquity, a hip condition often mistaken for congenital hip dislocation, affects newborns. Early detection and treatment are crucial for preventing long-term mobility issues.
Area of Science:
- Orthopedics
- Pediatric Medicine
- Developmental Biology
Background:
- Newborn screening for hip dysplasia has increased recognition of fixed pelvic obliquity.
- Pelvic obliquity involves restricted hip abduction on one side and adduction on the other.
- This condition can present with clinical signs mimicking congenital hip dislocation.
Purpose of the Study:
- To analyze the incidence and clinical characteristics of pelvic obliquity in infants with unilateral dysplastic hips.
- To evaluate the outcomes of untreated and treated pelvic obliquity.
Main Methods:
- Retrospective analysis of 192 consecutive cases of unilateral dysplastic hips treated between 1974-1978.
- Clinical examination to identify characteristic postural patterns.
- Documentation of treatment outcomes, including resolution, subluxation, dislocation, and long-term incapacity.
Main Results:
- 44% (23%) of infants with unilateral dysplastic hips were diagnosed with pelvic obliquity.
- The majority of affected infants were female (35) and firstborn (39).
- While 33 cases showed complete resolution within the first year, some cases persisted, leading to subluxation, dislocation, or long-term physical incapacity.
Conclusions:
- Pelvic obliquity is a significant finding in infants with unilateral hip dysplasia.
- Early diagnosis and intervention are vital to prevent severe complications and ensure optimal outcomes.
- The condition's varied progression highlights the need for continued monitoring and appropriate management strategies.
Abstract:
Screening of the newborn to detect hip dysplasia has led to the increasing recognition of fixed pelvic obliquity, in which one hip has restriction of abduction and the other, restriction of adduction. The hip with limited abduction is apparently short, so that the infant presents signs clinically indistinguishable from those of congenital dislocation. During the years 1974-78, 192 consecutive cases of unilateral dysplastic hips were treated by us; 44 (23%) were diagnosed as having pelvic obliquity. Nine were males and 35, females; 39 were firstborn. A characteristic postural pattern was found on examination. If untreated in the early stages, a morbid degree of subluxation developed and in six cases, complete dislocation occurred. In 33 cases, complete resolution of abduction contracture and subsequent pelvic obliquity occurred within the first year of life. In a number of cases, pelvic obliquity persisted for years and in a few, resulted in physical incapacity.
More Related Videos
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
 07:43
In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Related Concept Videos
 01:16
Bones of the Lower Limb: Femur and Patella
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:26
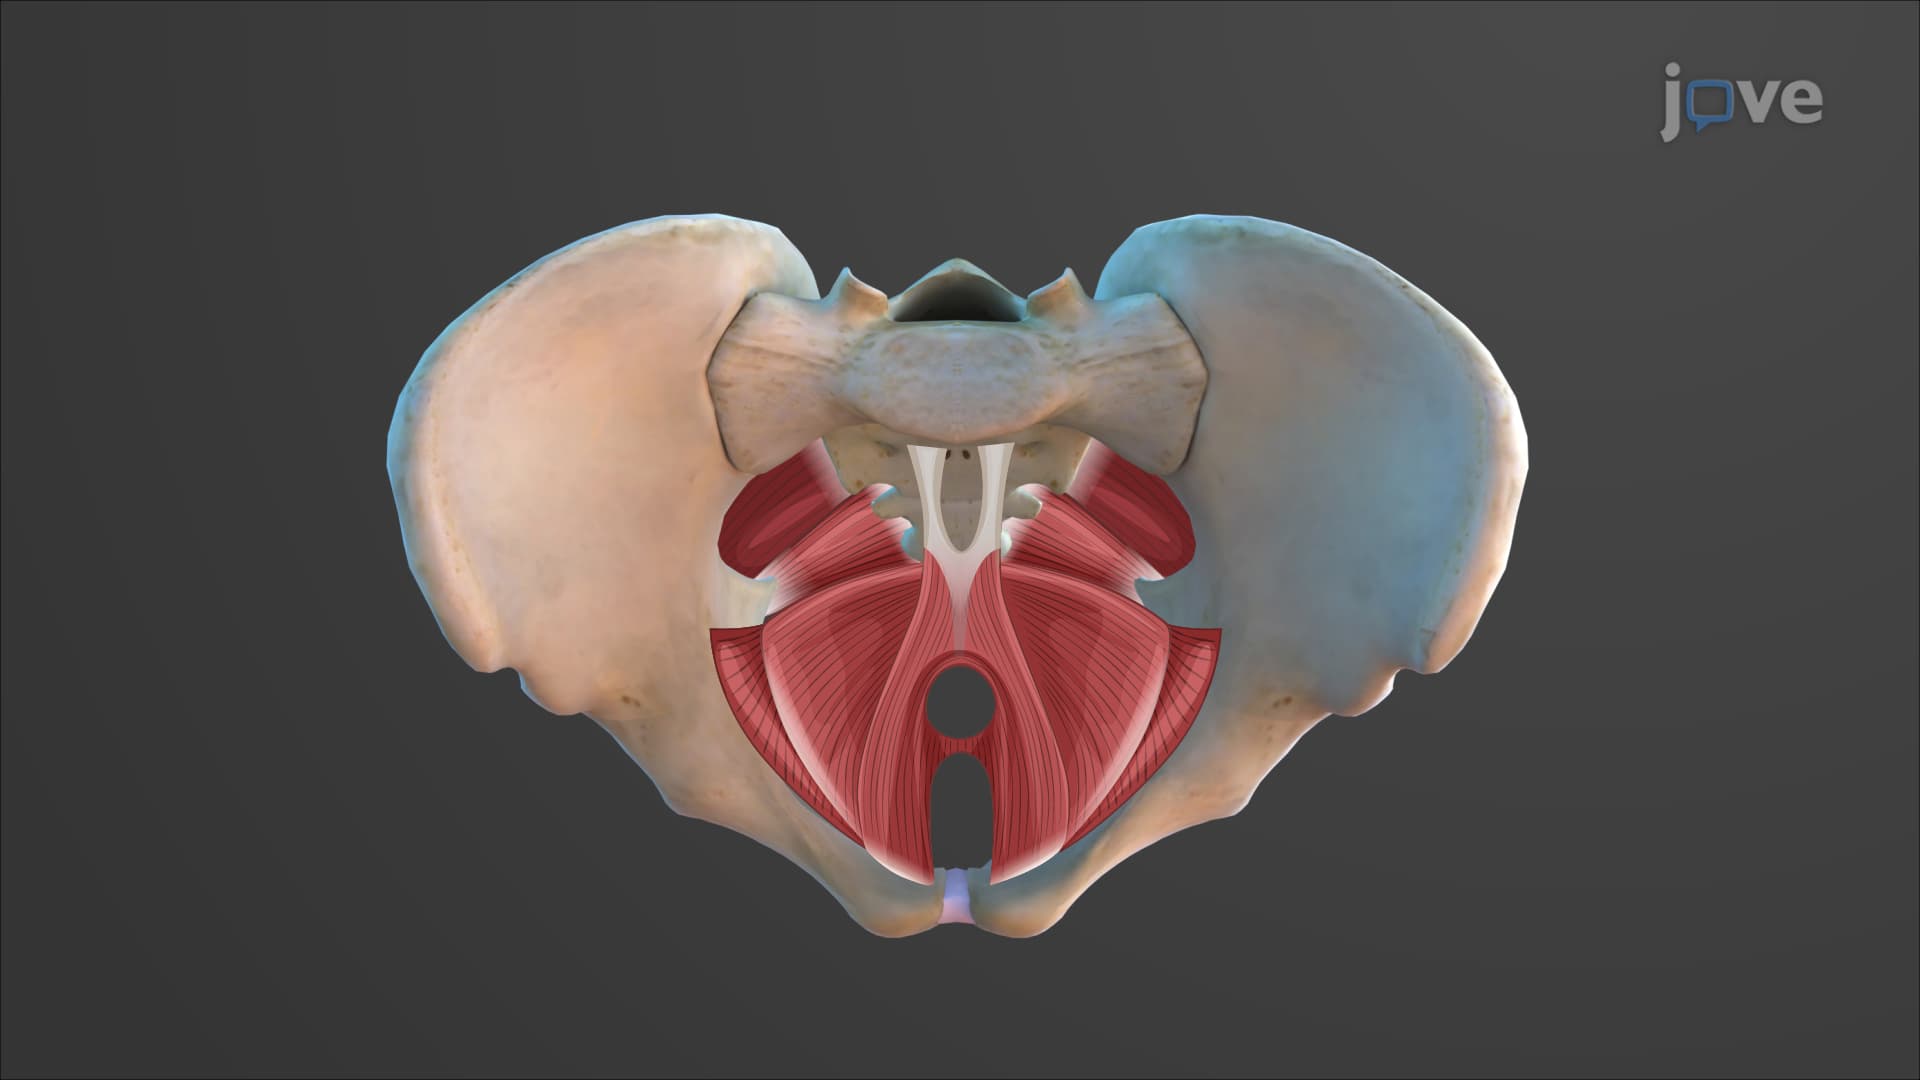
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:20
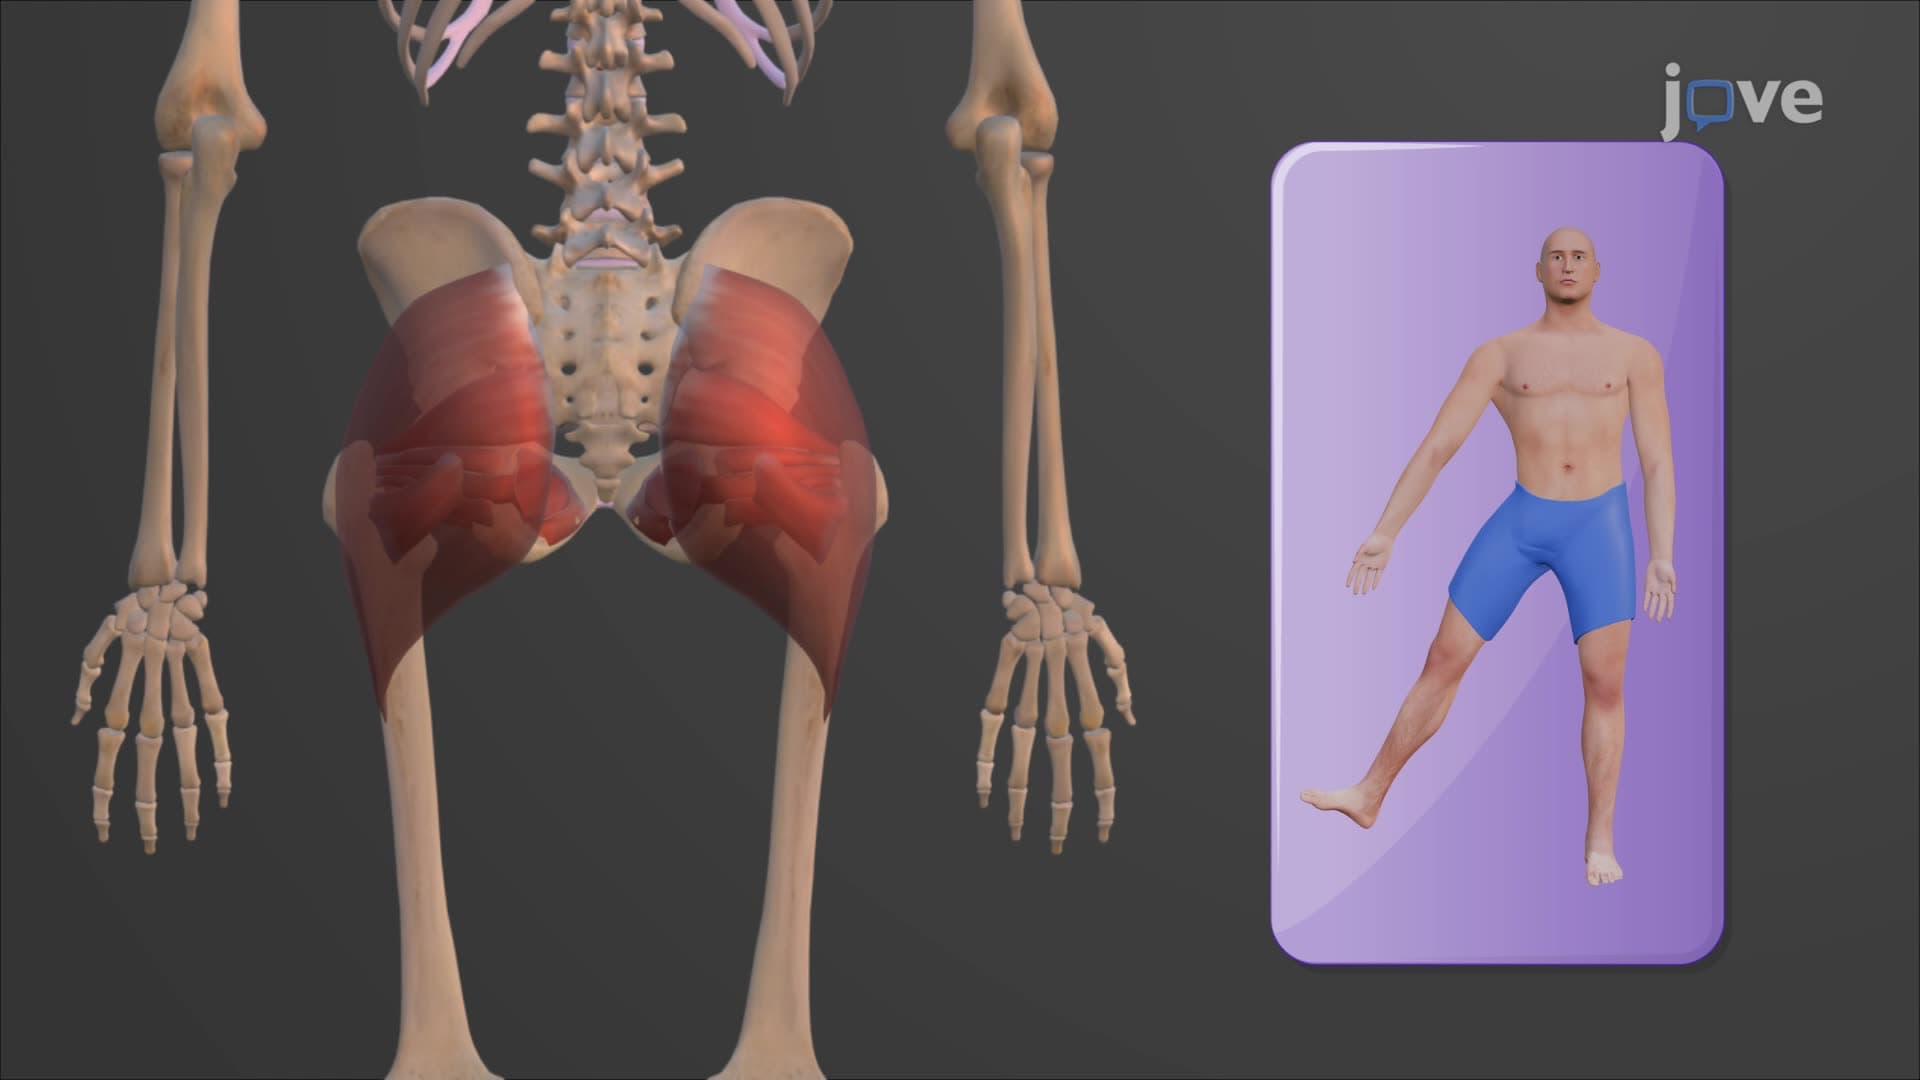
Muscles that Move the Thigh
Three other significant muscles are the gluteus maximus, gluteus medius, and gluteus minimus. The gluteus maximus originates from the posterior surface of the ilium, sacrum, and coccyx, and the thoracolumbar...