Related Experiment Video
Updated: Jul 30, 2026


In Vitro Aggregation Assays Using Hyperphosphorylated Tau Protein
Published on: January 2, 2015
Detection of D-aspartate in tau proteins associated with Alzheimer paired helical filaments
1Department of Pathology, Albert Einstein College of Medicine, Bronx, NY 10461, USA.

Abstract:
Paired helical filaments (PHF) characteristic of Alzheimer neurofibrillary lesions are known to contain a modified form of microtubule associated protein tau. These proteins, PHF-tau, differ from normal tau in the extent and the site of phosphorylation. To determine whether PHF-tau, tau proteins from normal adult brains (N-tau), tau proteins from Alzheimer brains not associated with PHF (A-tau), and tau proteins from fetal brains (F-tau) differ in racemization, these proteins were compared for their D-aspartate content. The results demonstrated that PHF-tau contain more D-aspartate than N-tau, A-tau and F-tau. The average percentage D-aspartate for these proteins, after a correction for background, are 4.9%, 2.8%, 1.6%, and 1% for PHF-tau, N-tau, A-tau and F-tau, respectively. It remains to be determined if the increase in D-aspartate is a consequence of PHF formation. It is also unknown if the change in D-aspartate content in PHF-tau is associated with phosphorylation, which alters the susceptibility of tau to proteolysis.
Insights
Paired helical filaments-tau (PHF-tau) in Alzheimer's disease show increased D-aspartate levels compared to normal tau. This suggests a potential link between tau racemization and neurofibrillary tangle formation.
Area of Science:
- Neuroscience
- Biochemistry
- Alzheimer's Disease Research
Background:
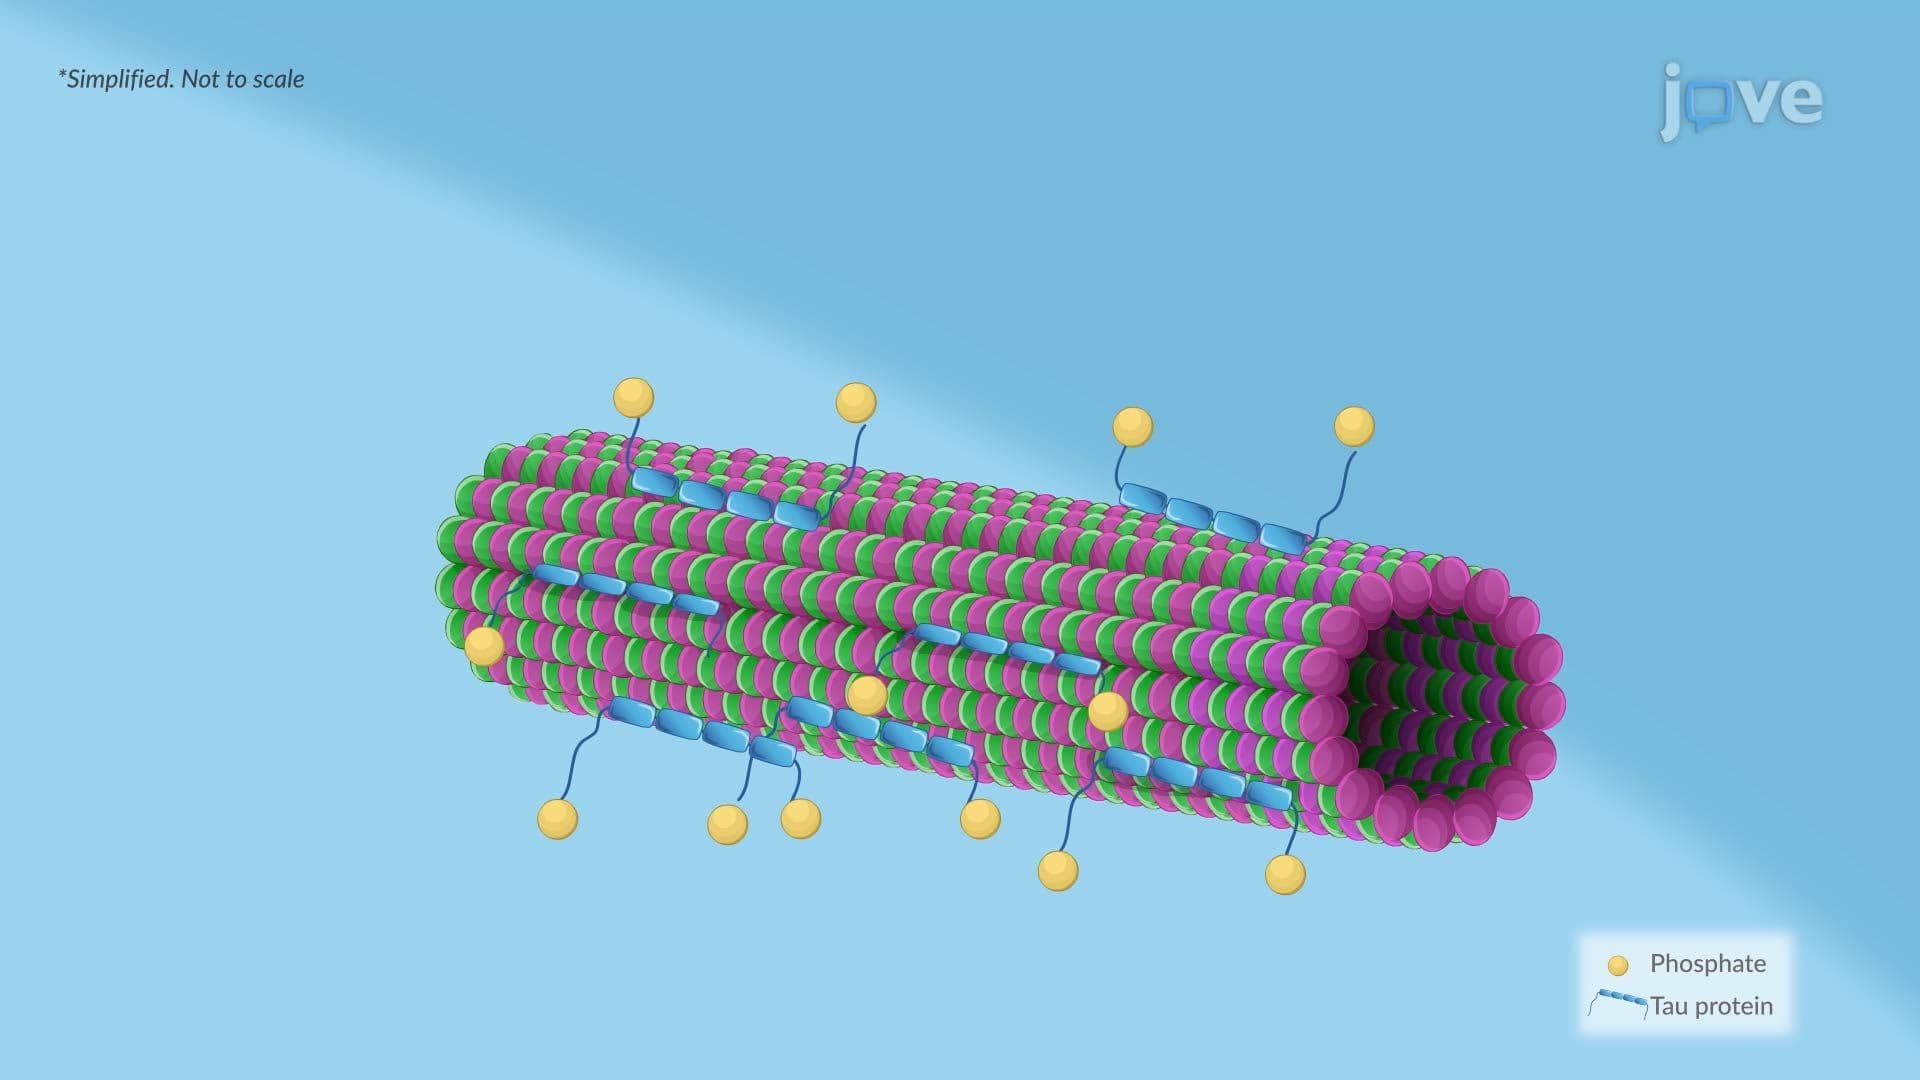
- Paired helical filaments (PHF) in Alzheimer's disease neurofibrillary lesions contain modified tau proteins (PHF-tau).
- PHF-tau differs from normal tau (N-tau) in phosphorylation extent and site.
- Alzheimer's-associated tau (A-tau) and fetal tau (F-tau) also exist for comparison.
Purpose of the Study:
- To investigate differences in racemization, specifically D-aspartate content, among PHF-tau, N-tau, A-tau, and F-tau.
- To determine if increased D-aspartate is linked to PHF formation in Alzheimer's disease.
Main Methods:
- Quantification of D-aspartate content in isolated tau protein fractions.
- Comparison of D-aspartate percentages across different tau types (PHF-tau, N-tau, A-tau, F-tau).
Main Results:
- PHF-tau exhibited significantly higher D-aspartate content (4.9%) compared to N-tau (2.8%), A-tau (1.6%), and F-tau (1%).
- Background correction was applied for accurate D-aspartate percentage determination.
Conclusions:
- Alzheimer's disease PHF-tau shows elevated levels of D-aspartate, indicating increased protein racemization.
- The relationship between increased D-aspartate, PHF formation, and tau phosphorylation requires further investigation.


Related Concept Videos
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:23
Alzheimer Disease ll: Pathophysiology
 01:22
Dementia l: Introduction