Related Experiment Video
Updated: Jun 27, 2026
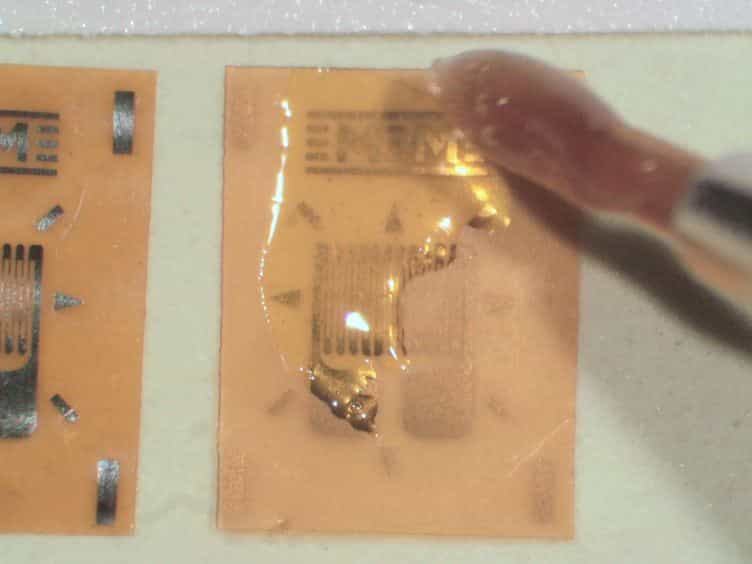

Fabrication and Implantation of Miniature Dual-element Strain Gages for Measuring In Vivo Gastrointestinal Contractions in Rodents.
Published on: September 18, 2014
Gastric ammonia has a potent ulcerogenic action on the rat stomach
M Murakami1, H Saita, S Teramura
1Department of Geriatric Medicine, Faculty of Medicine, Kyoto University, Japan.

Background:
The pathophysiological mechanism by which Helicobacter pylori induces mucosal injury has not been clarified. The aim of this study was to investigate the role of urea, urease, and ammonia in rat gastric mucosal lesions using an ex vivo chamber model.
Methods:
Two groups of rats, normotensive rats and those subjected to ischemia, were studied. The gastric mucosa was examined histologically and macroscopically, and the transmucosal potential difference was measured.
Results:
Instillation of urea into the stomach generated ammonia in the presence of urease. The amount of ammonia was increased depending on the concentration of urea and was closely associated with the severity of the histological lesions. The exposure of the stomach to 15-60 mmol/L ammonium hydroxide induced both a reduction in transmucosal potential difference and microscopic damage to the gastric mucosa in normotensive rats. Moreover, 15-60 mmol/L ammonium hydroxide produced severe macroscopic gastric lesions in the rats subjected to ischemia.
Conclusions:
These results show that ammonia is deleterious to the gastric mucosa and suggest the importance of urea, urease, and ammonia in the pathophysiology of gastric diseases in H. pylori-infected patients.


Related Concept Videos
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
 01:28
Acid Suppressive Drugs for Peptic Ulcer Disease: Histamine H2-Receptor Antagonists
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:24
Peptic Ulcer Disease II: Pathophysiology