Related Experiment Video
Updated: Aug 11, 2026

Cell-based Assay Protocol for the Prognostic Prediction of Idiopathic Scoliosis Using Cellular Dielectric Spectroscopy
Published on: October 16, 2013
Infantile scoliosis in Marfan syndrome
P D Sponseller1, N Sethi, D E Cameron
1Department of Orthopaedic Surgery, Johns Hopkins University, Baltimore, Maryland, USA.

Insights
Infantile scoliosis in Marfan syndrome is severe, with bracing showing limited effectiveness. Surgical fusion yields better results in older children, but cardiac complications remain a significant concern.
Area of Science:
- Genetics and Skeletal Dysplasias
- Pediatric Orthopedics
- Cardiology
Background:
- Marfan syndrome is a genetic disorder affecting connective tissue, often leading to skeletal and cardiovascular issues.
- Infantile scoliosis in Marfan syndrome is poorly understood, with limited data on its characteristics and treatment outcomes.
- This study addresses a gap in knowledge regarding the presentation and management of scoliosis in young Marfan syndrome patients.
Purpose of the Study:
- To characterize infantile scoliosis in patients with Marfan syndrome.
- To evaluate the effectiveness of different treatment modalities for this condition.
- To identify optimal timing and approaches for surgical intervention.
Main Methods:
- Retrospective review of clinical data from patients diagnosed with Marfan syndrome and scoliosis before age three.
- Analysis of skeletal and general features, family history, and treatment responses in a cohort of 14 patients.
- Evaluation of outcomes for bracing, instrumentation without fusion, and instrumented spinal fusion.
Main Results:
- Most patients (13/14) lacked a family history of Marfan syndrome, deviating from the typical autosomal dominant inheritance.
- All patients exhibited Marfanoid habitus, and most had significant cardiac (valvular insufficiency, aortic aneurysm) and skeletal (lens dislocation, sternal deformity) issues.
- Bracing was ineffective in halting curve progression; spinal fusion showed better correction (51%) in older children (mean age 6.6 years), though long-term correction was limited (20% at 5 years).
Conclusions:
- Bracing is minimally effective for severe infantile scoliosis in Marfan syndrome, recommended only for curves <40 degrees.
- Surgery is advised for patients older than four years due to high risk of fatal cardiac complications in younger children.
- Instrumented fusion offers better outcomes in older patients (>5 years) without significant kyphosis; instrumentation without fusion is suitable for select cases.
Study Design:
A retrospective review of clinical data was conducted.
Objectives:
To determine the characteristics of infantile scoliosis in Marfan syndrome and the response to treatment of patients with this condition.
Summary Of Background Data:
No previous study has reported the features of this condition nor the effect of treatment on patients with this syndrome.
Methods:
The data on all patients seen at one institution who had Marfan syndrome and scoliosis by age three were reviewed. Fourteen of the 600 patients from the group examined who had Marfan syndrome fit the above criteria. Skeletal and general features were studied.
Results:
Thirteen of the 14 patients had no family history of Marfan syndrome, a finding which does not fit the usual autosomal dominant inheritance pattern. All 14 patients had exaggeration of the Marfan. All but one patient had cardiac valvular insufficiency that required repair by age 11. Thirteen patients had thoracic aortic aneurysm, 10 had lens dislocation, and eight had sternal deformity. Three patients had hip dislocations, two had pyloric stenosis, and two had dural ectasia. Motor delay was evidenced by onset of walking past 18 months in nine patients; three of these patients were never able to walk independently. One patient each died at ages 1, 3, 4, and 8 years; all others have survived to present (mean age, 13 years). The mean curve of the patients' spines at presentation was 38 degrees. Eleven curves were double major, two were thoracolumbar, and one was double thoracic. Brace wear did not halt curve progression in any of the nine patients for whom it was used. Instrumentation without fusion was used in three patients for a mean of 3 years, with best results in one nonkyphotic curve. Nine patients underwent instrumented fusion at a mean age of 6.6 years (range, 3-13 years). Mean curve correction was 51% (from 72 degrees to 34 degrees). Final mean curve was 54 degrees for a mean correction of 20% at the 5-year (average, 5.4 years) follow-up examination. Acute complications occurred in three patients, and five patients needed a second surgery for late complications. Causes for curve increase after surgery included growth and loss of fixation.
Conclusions:
In this most severe form of Marfan syndrome, bracing has a limited role and is only to be used if the curve is less than 40 degrees. Surgery should not be performed on a patient younger than four years of age because many patients with large curves before this age will succumb spontaneously to cardiac complications. Instrumentation without fusion should be considered only for patients with no significant kyphosis. Results of fusion are better for patients who are older than five years of age.
More Related Videos

Related Concept Videos
 01:16
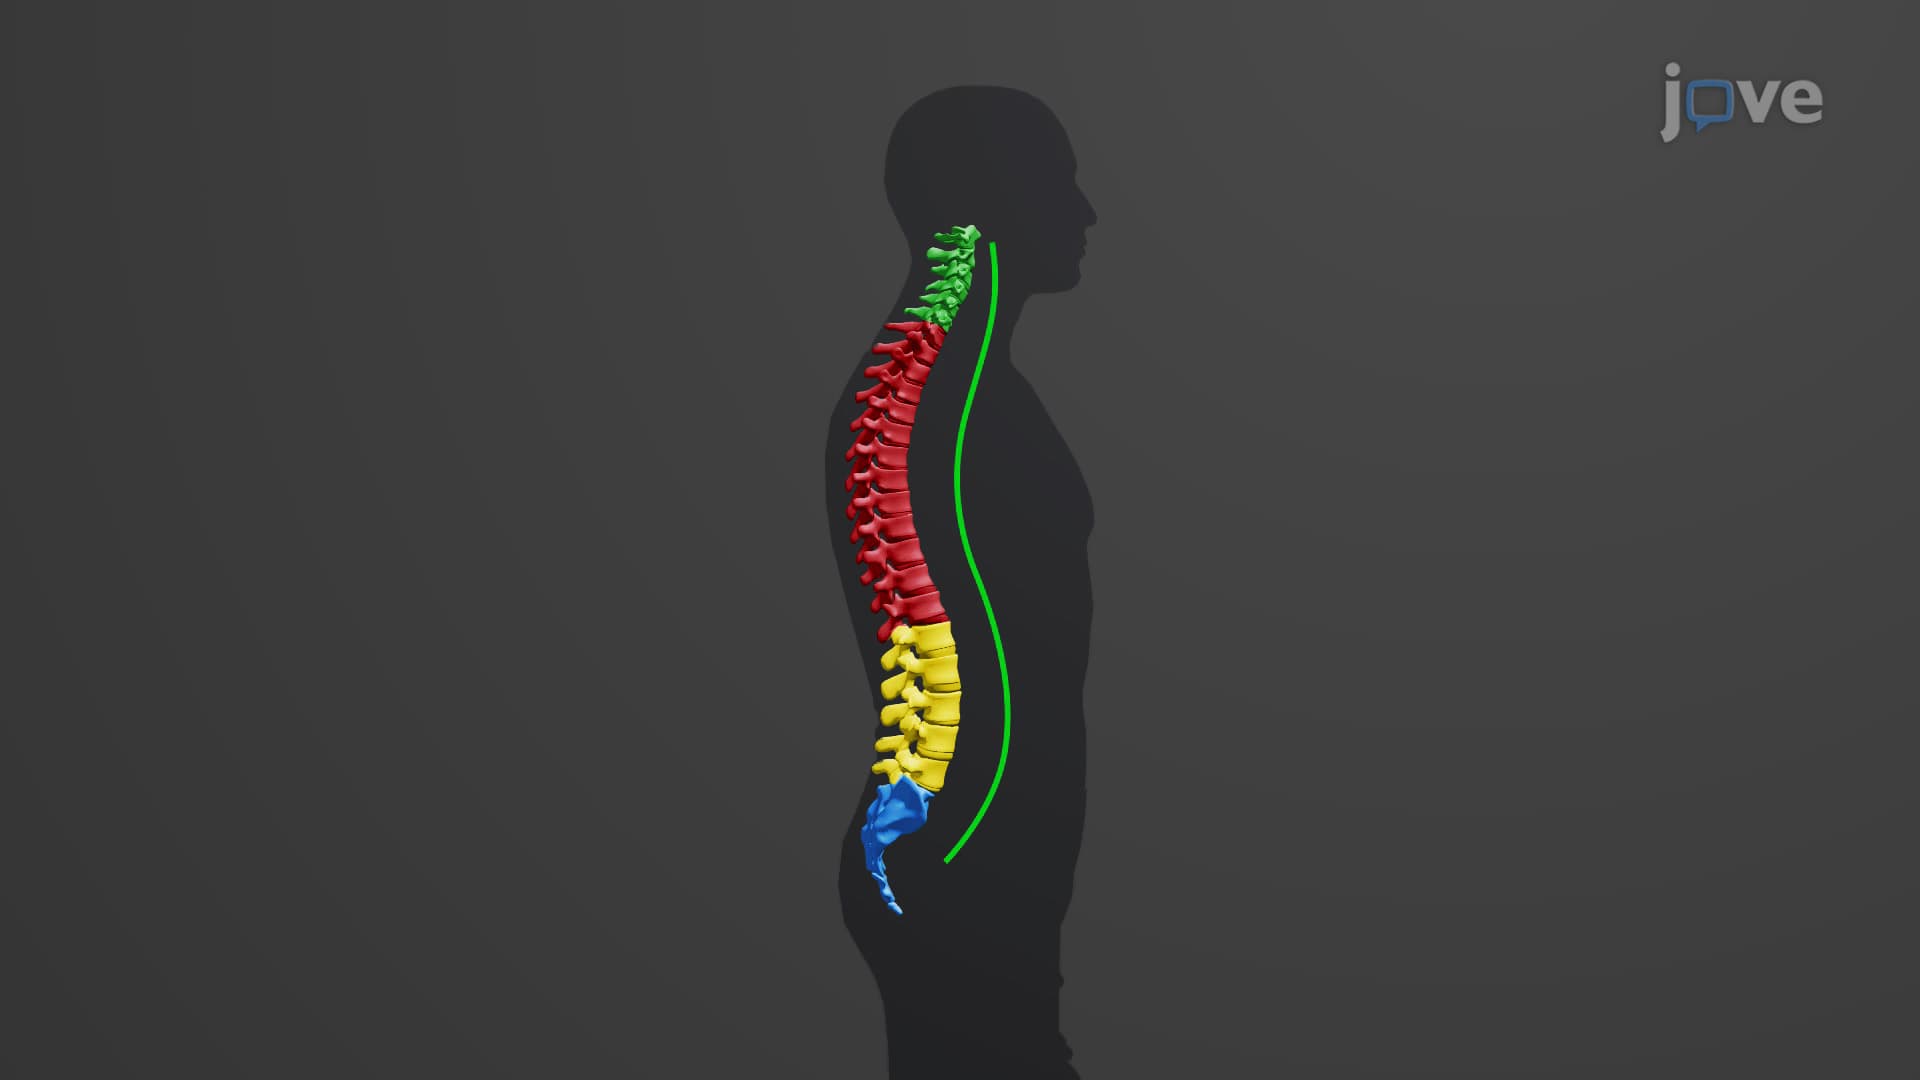
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:28
Disorders of the Skeletal Muscle
Musculoskeletal disorders
Musculoskeletal disorders involve injuries and conditions affecting the skeletal muscles and associated connective tissues. These disorders can arise from acute biomechanical stresses or chronic overuse and can occur across different age groups. Common injuries include sprains, fractures, and muscular strains, often resulting from...
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation, but...
 01:27
Mitral Valve Prolapse I: Introduction
 01:22
Mitral Stenosis I: Introduction
 01:30
Aneurysm I: Introduction