Related Experiment Video
Updated: Oct 2, 2026
Invasive Hemodynamic Characterization of the Portal-hypertensive Syndrome in Cirrhotic Rats
Published on: August 1, 2018
[Are diuretics in the treatment of portal hypertension rational?]
1Institut für Klinische Pharmakologie der Universität Bern.

Abstract:
When ascites develops in a patient with cirrhosis his probability to survive the following 2 years amounts to 50%. It is determined essentially by the residual functional capacity of the liver. In 80 to 90% of patients ascites due to portal hypertension can be managed by salt restriction and diuretics. Aldosterone-antagonists are more efficient and have fewer side effects than loop diuretics. They may lower portal tension by an additional direct effect on the vasculature. A daily reduction of body weight of 0.5 to 0.75 kg should not be exceeded because (prerenal) renal failure may become a threat. If diuretics are insufficient or when a rapid therapeutic success is needed paracentesis of 4-6.1 is a safe option if intravascular volume is substituted simultaneously. Albumin has proven superior to other plasma expanders (protection of renal function, survival). Only in the few patients whose ascites is intractable by the forementioned measures should alternatives such as peritoneo-, venous or porto-systemic shunts (nowadays mostly by interventional techniques via a transjugular catheter) be evaluated. The only treatment which not only attacks ascites symptomatically but also corrects the underlying disease is liver transplantation.
More Related Videos


Related Concept Videos
 01:16
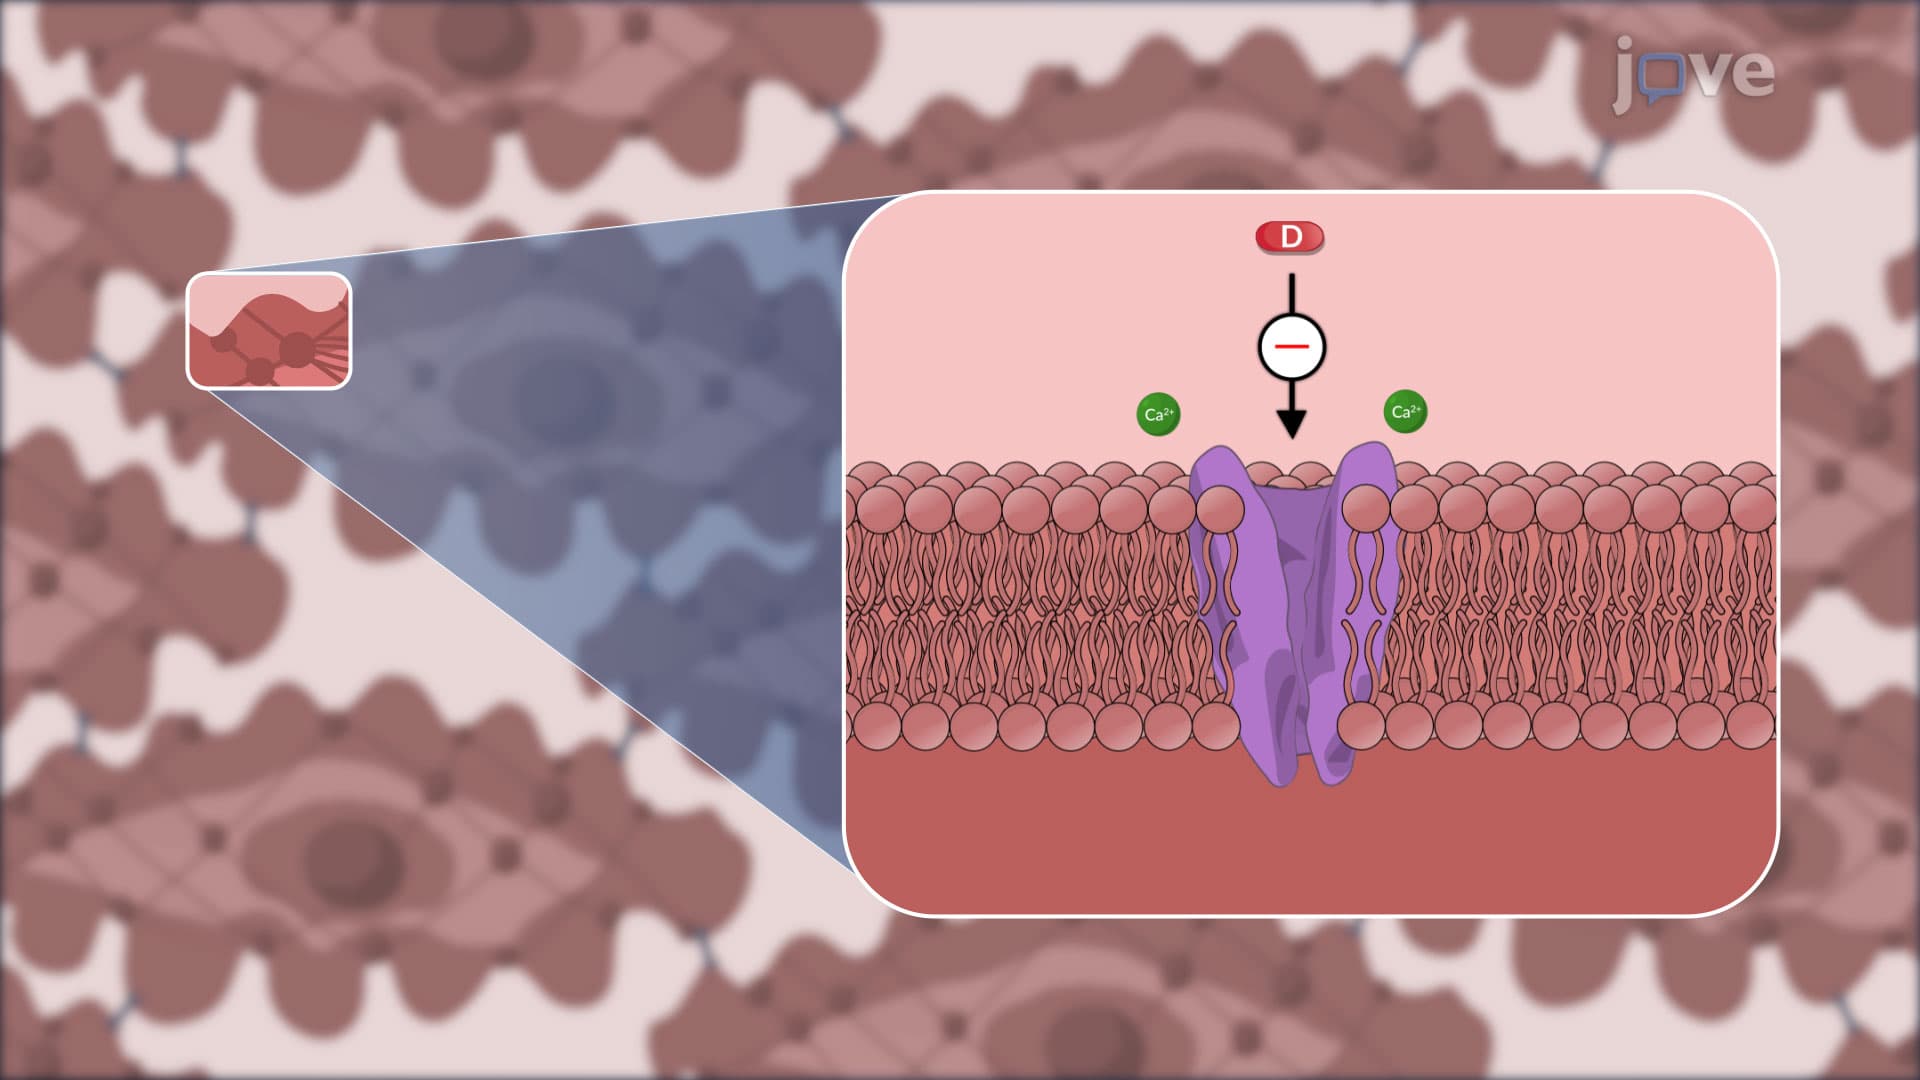
Antihypertensive Drugs: Action of Diuretics
 01:15
Antihypertensive Drugs: Thiazide-Class Diuretics
 01:22
Heart Failure Drugs: Diuretics
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:30
Heart Failure V: Medical Management
 01:22
Portal Hypertension