Related Experiment Video
Updated: Oct 5, 2026
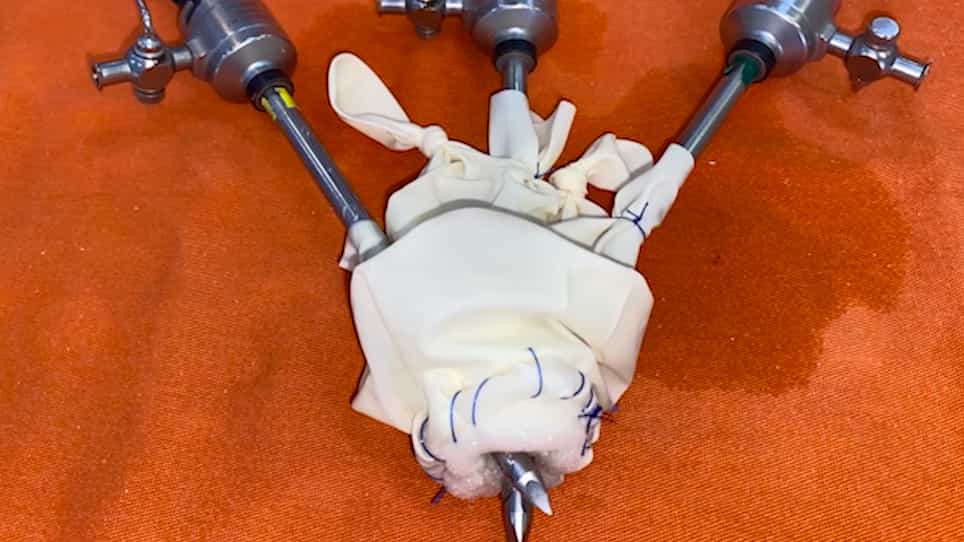
Low-Cost Single-Port (LoCoSP) Device for a Transcervical Approach in Minimally Invasive Transhiatal Esophagectomy
Published on: September 11, 2021
Type IV laryngotracheoesophageal clefts -- recent 5 year experience at Great Ormond Street Hospital for Children
1Manchester Children's Hospital-Booth Hall, Charlestown Road, Blackley, Manchester M9 2DD, UK. zpshehab@hotmail.com

Insights
Type IV laryngotracheoesophageal clefts are rare but survivable. Early diagnosis and specialized surgical intervention improve outcomes for affected infants.
Area of Science:
- Pediatric Surgery
- Congenital Anomalies
- Otolaryngology
Background:
- Laryngotracheoesophageal clefts (LTECs) are rare congenital anomalies.
- Type IV LTEC represents the most severe form, involving a complete separation of the larynx, trachea, and esophagus.
- Management of Type IV LTEC is challenging, with high mortality rates.
Observation:
- This article reviews a 5-year experience with six infants diagnosed with Type IV LTEC at a specialized pediatric center.
- Two of the six infants achieved long-term survival.
- Literature review on complicating issues and management strategies was performed.
Findings:
- Successful surgical repair and long-term survival are possible with a standardized approach.
- Recognition of specific complicating factors is crucial for effective management.
- Early diagnosis and aggressive, planned surgical intervention are key.
Implications:
- Increased awareness and timely diagnosis of Type IV LTEC can reduce mortality.
- Centralization of care in pediatric expertise centers is recommended.
- A standardized approach to surgical repair may improve survival rates for this rare condition.
Abstract:
This article summarises a 5 year experience of type IV laryngotracheoesophageal clefts from Great Ormond Street Hospital for Children, London. We present six infants who had type IV clefts, two of whom are long-term survivors, and we review the literature. The recognition of specific complicating issues may lead to a standardised approach, which can result in successful repair and long-term survival. Increased awareness of the condition and early diagnosis combined with aggressive, planned surgical intervention in centres of paediatric expertise should result in a significant reduction of current mortality.

Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:27
Esophageal Achalasia
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...