Related Experiment Video
Updated: Sep 20, 2026
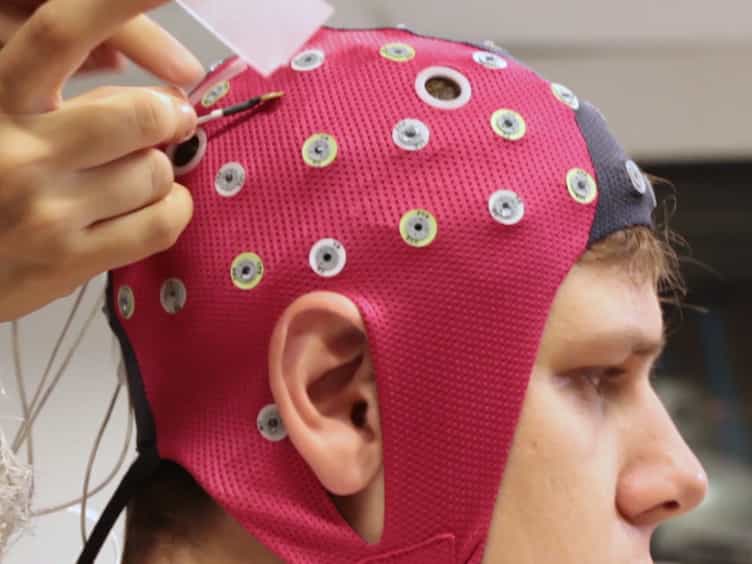

Recording Brain Electromagnetic Activity During the Administration of the Gaseous Anesthetic Agents Xenon and Nitrous Oxide in Healthy Volunteers
Published on: January 13, 2018
Computerize anesthesia record keeping in thoracic surgery--suitability of electronic anesthesia records in evaluating
Jochen Sticher1, Axel Junger, Bernd Hartmann
1Department of Anaesthesiology, Intensive Care, and Pain Management, University Hospital Giessen, Germany.

Objective:
The aim of this retrospective study was to assess the suitability of routine data gathered with a computerized anesthesia record keeping system in investigating predictors for intraoperative hypoxemia (SpO2 < 90%) during one-lung ventilation (OLV) in pulmonary surgery.
Methods:
Over a four-year period data of 705 patients undergoing thoracic surgery (pneumonectomy: 78; lobectomy: 292; minor pulmonary resections: 335) were recorded online using an automated anesthesia record-keeping system. Twenty-six patient-related, surgery-related and anesthesia-related variables were studied for a possible association with the occurrence of intraoperative hypoxemia during OLV. Data were analyzed using univariate and multivariate (logistic regression) analysis (p < 0.05). The model's discriminative power on hypoxemia was checked with a receiver operating characteristic (ROC) curve. Calibration was tested using the Hosmer-Lemeshow goodness-of-fit test.
Results:
An intraoperative incidence of hypoxemia during OLV was found in 67 patients (9.5%). Using logistic regression with a forward stepwise algorithm, body-mass-index (BMI, p = 0.018) and preoperative existing pneumonia (p = 0.043) could be detected as independent predictors having an influence on the incidence of hypoxemia during OLV. An acceptable goodness-of-fit could be observed using cross validation for the model (C = 8.21, p = 0.370, degrees of freedom, df 8; H = 3.21, p = 0.350, df 3), the discriminative power was poor with an area under the ROC curve of 0.58 [0.51-0.66].
Conclusions:
In contrast to conventional performed retrospective studies, data were directly available for analyses without any manual intervention. Due to incomplete information and imprecise definitions of parameters, data of computerized anesthesia records collected in routine are helpful but not satisfactory in evaluating risk factors for hypoxemia during OLV.

Related Concept Videos
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...