Related Experiment Video
Updated: Aug 9, 2026
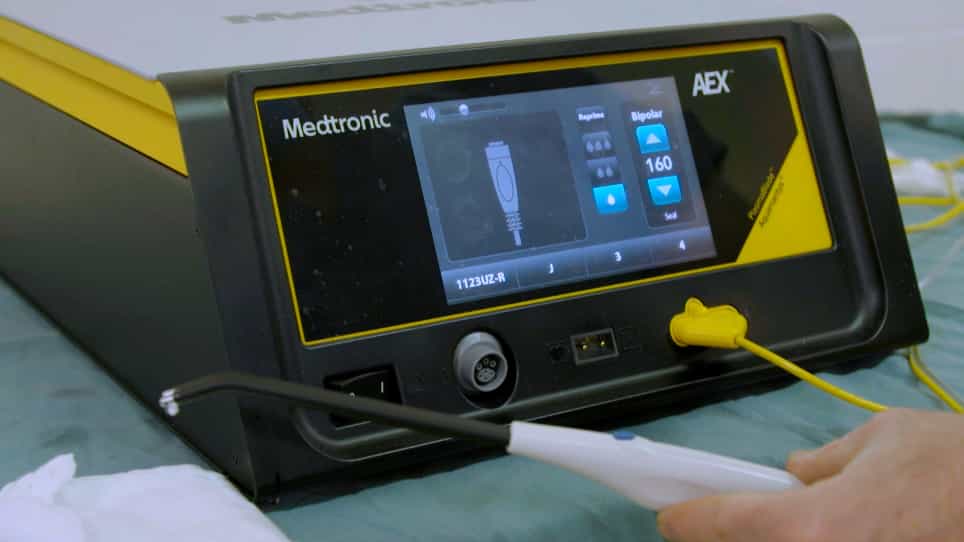

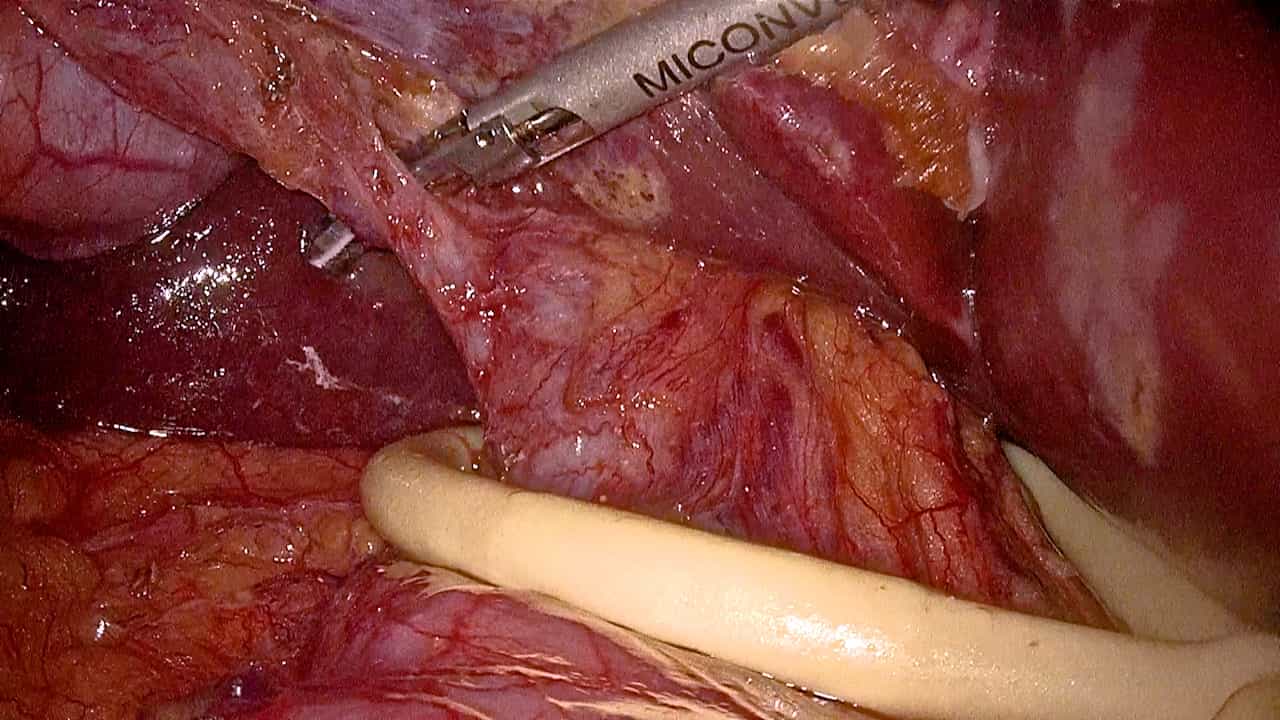
A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Hepatic trauma: contemporary management
1Department of Surgery, Oregon Health and Science University, L223, 3181 SW Sam Jackson Park Road, Portland, OR 97201-3098, USA. trunkeyd@ohsu.edu

In the introduction, I posed several questions that were issues/controversies. The answers will probably be interpreted as equally controversial. I do not believe there is strong evidence that the incidence of liver injuries has increased. Diagnostic modalities have contributed to this seeming increase, as well as population increases and the concentration of severe liver injuries in trauma centers, now present in 35 states. I believe there are more blunt injuries now, relative to penetrating injuries. The peak of penetrating injuries occurred in the 1970s and 1980s and lasted almost 2 decades. I believe some authors are overly enthusiastic for nonoperative management. I am particularly critical of authors who do not include all components of the surgical armamentarium into their treatment of severe liver injuries. I also believe that the complications following nonoperative management are currently unacceptable, as documented in the references. I have shared with you the strategies for operative management, but there are equally good or better strategies in the surgical literature.
In the introduction, I posed several questions that were issues/controversies. The answers will probably be interpreted as equally controversial. I do not believe there is strong evidence that the incidence of liver injuries has increased. Diagnostic modalities have contributed to this seeming increase, as well as population increases and the concentration of severe liver injuries in trauma centers, now present in 35 states. I believe there are more blunt injuries now, relative to penetrating injuries. The peak of penetrating injuries occurred in the 1970s and 1980s and lasted almost 2 decades. I believe some authors are overly enthusiastic for nonoperative management. I am particularly critical of authors who do not include all components of the surgical armamentarium into their treatment of severe liver injuries. I also believe that the complications following nonoperative management are currently unacceptable, as documented in the references. I have shared with you the strategies for operative management, but there are equally good or better strategies in the surgical literature.
More Related Videos

Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:26
Pharmaceutical Poisoning: Treatment Strategies
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:22
Acute Kidney Injury VI: Nursing Management