Related Experiment Video
Updated: Aug 24, 2026
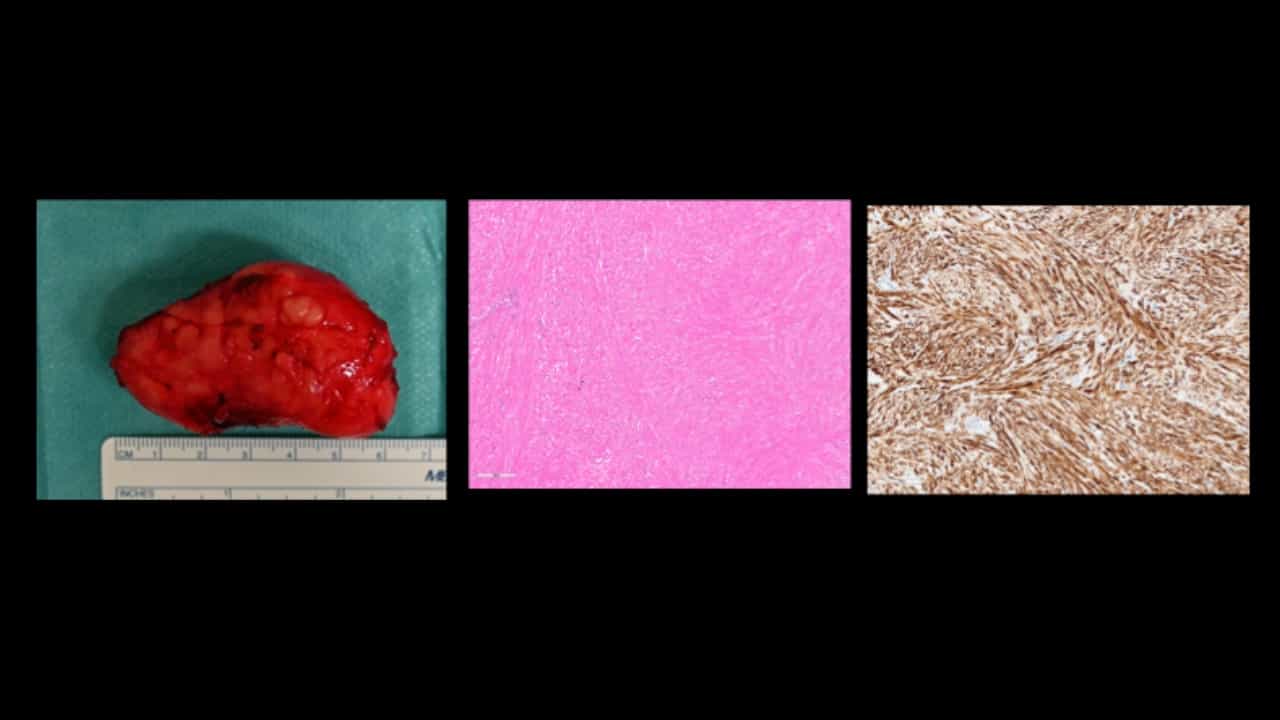

Robotic Enucleation of Esophageal Leiomyoma
Published on: February 20, 2026
Aromatase and leiomyoma of the uterus
Makio Shozu1, Kouich Murakami, Masaki Inoue
1Department of Obstetrics and Gynecology, Kanazawa University School of Medicine, Kanazawa, Japan.

Abstract:
In leiomyoma of the uterus, both aromatase and 17beta-hydroxysteroid dehydrogenase (17beta-HSD) type I are overexpressed compared with myometrium. This suggests that leiomyoma cells convert circulating androstenedione into estrone (via aromatase), then into the active form of estrogen, estradiol (via 17beta-HSD type I). In vitro experiments and several clinical findings support the notion that in situ estrogen plays a role in leiomyoma growth under hypoestrogenemic conditions, such as natural menopause and therapy with gonadotropin-releasing hormone (GnRH) agonists. GnRH agonists abolish estrogen production both in situ in leiomyoma and in the ovary, leading to quick and profound regression of the leiomyoma. Aromatase inhibitors also inhibit estrogen synthesis in both leiomyoma and the ovary and may be used therapeutically. Certain doses of competitive aromatase inhibitors would completely inhibit estrogen production in leiomyoma, whereas ovarian production of estrogen would continue at reduced levels. This may lead to advantageous therapeutic conditions in which leiomyoma regresses without adverse symptoms related to estrogen depletion because levels of ovarian estrogen would be insufficient to support leiomyoma growth but sufficient to prevent symptoms associated with deficiency. This article discusses the potential uses of aromatase inhibitors.