Related Experiment Video
Updated: Jul 11, 2026

Murine Model of Allergen Induced Asthma
Published on: May 14, 2012
Assessment of airway function in young children with asthma: comparison of spirometry, interrupter technique, and
J Black1, A D G Baxter-Jones, J Gordon
1Department of Child Health, University of Aberdeen, Aberdeen, Scotland, UK.

Abstract:
The assessment of airway function in young children requires adaptation of techniques designed for adults and/or application of techniques that do not require complex respiratory maneuvers. We sought to assess two methods of measuring airway function: time to peak expiratory flows as a ratio of expiratory time (T(PTEF)/T(E)), derived from respiratory inductance plethysmography, and total respiratory resistance by the interrupter technique (Rint), both obtained during quiet tidal breathing. Both techniques were referenced to FEV1 and flow at 50% expired volume (FEF50) from conventional spirometry in 30 children aged 4-8 years (median age, 6.9; range, 4.5-8.5 years) with a physician diagnosis of asthma and who were able to perform FEV1 with a repeatability of at least 8%. T(PTEF)/T(E) and Rint were performed in random order followed by spirometry, in order to reduce the possible effects of pulmonary stretch on tidal breathing measures. Coefficients of variation (CV) and mean absolute change/baseline standard deviation were derived for each measurement. Baseline FEV1 did not correlate significantly with T(PTEF)/T(E) (r = 0.025), but did correlate with Rint (r = 0.737, P < 0.001); respective relationships for change after bronchodilator were r = 0.09 (ns) and r = 0.64 (P < 0.001). FEF50 also correlated significantly with Rint (R = 0.769, P < 0.001) but not with T(PTEF)/T(E). FEV1 and FEF50 both increased postbronchodilator, with respective mean changes of 11.4% and 28% (P < 0.001), while Rint decreased by 24.3% (P < 0.001). No significant changes were noted for T(PTEF)/T(E). T(PTEF)/T(E) derived from inductance plethysmography does not detect mild airway obstruction or modest changes in airway caliber following bronchodilator in young children with asthma. The interrupter technique may have a role in assessing baseline airway function and response to therapy in children unable to perform reliable spirometry, and/or when the investigator wishes to avoid the possible influence of forced maneuvers on airway tone.
Related Concept Videos
 01:15
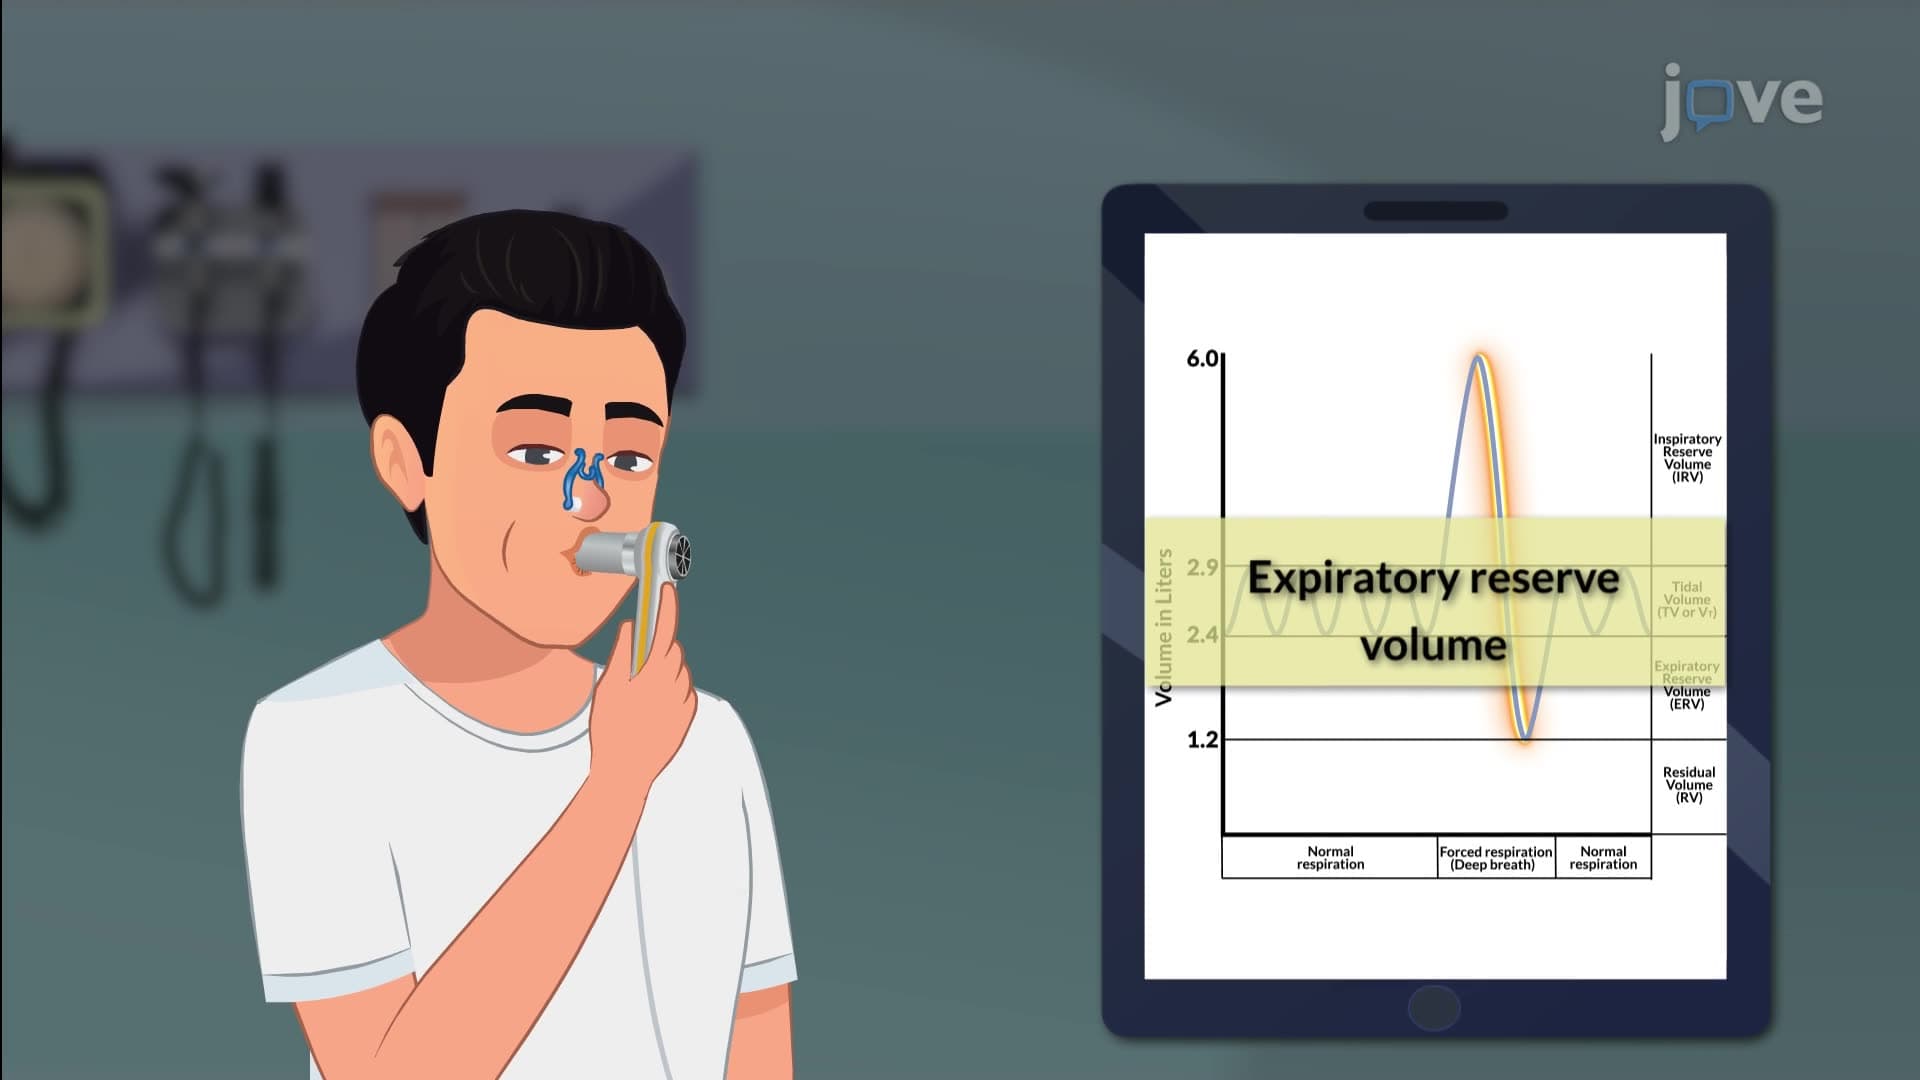
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:24
Physical Assessment of the Respiratory Tract II: Palpation
Thoracic Palpation
Thoracic palpation detects tenderness, masses, lesions, respiratory excursions, and vocal fremitus. The nurse assesses...
 01:28
Physical Assessment of the Respiratory Tract IV: Auscultation
Breath Sounds
Breath sounds are categorized into vesicular, bronchovesicular, and bronchial.
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...