Related Experiment Video
Updated: Jun 6, 2026
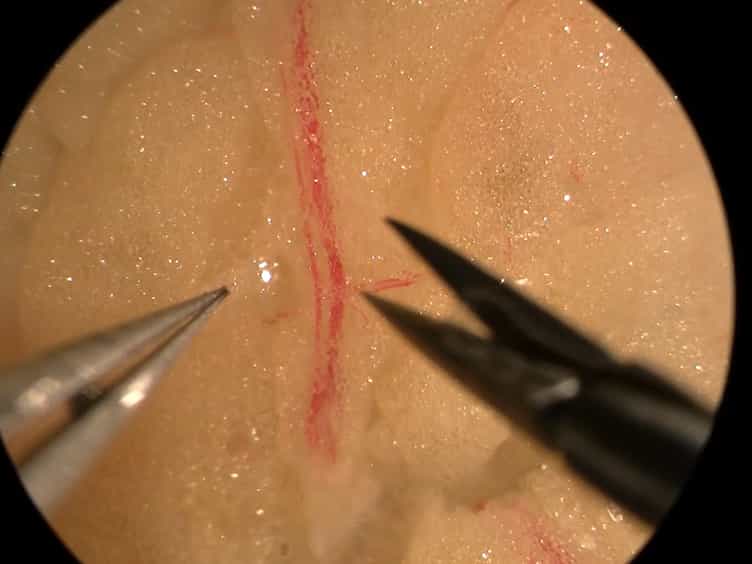
Assessment of Human Adipose Tissue Microvascular Function Using Videomicroscopy
Published on: September 29, 2017
Differential constrictor responses of cephalic and caudal vasculature to α-adrenoceptor agonist after hind limb
Simon R Hutchings1, Jong Moo Kim, Dongzhe Song
1Department of Anesthesiology, Pharmacology, and Therapeutics, Faculty of Medicine, The University of British Columbia, 2176 Health Sciences Mall, Vancouver, BC V6T 1Z3, Canada.

Abstract:
We examined the effects of hind limb unloading (HLU, 14 days) on constriction of carotid and iliac arterial beds in vivo in thiobutabarbital-anaesthetized rats and isolated carotid and iliac arteries in vitro. Both control and HLU rats had similar arterial pressure and carotid and iliac arterial flows. The HLU rats had increased carotid arterial but reduced iliac arterial constriction in response to methoxamine (α1-adrenoceptor agonist) in vivo. In contrast, constriction in response to methoxamine was reduced in the isolated carotid and unchanged in the iliac artery of HLU rats relative to control rats. Thus, HLU is associated with increased constriction of carotid arterial bed but reduced constriction of the isolated carotid artery, and reduced constriction of iliac arterial bed but unchanged constriction of the isolated iliac artery. These results show differential influence of HLU on constriction of cephalic and caudal arterial beds, and differential effect on constrictions of arterial beds relative to conduit arteries.
More Related Videos
 08:41
Assessment of Vascular Tone Responsiveness using Isolated Mesenteric Arteries with a Focus on Modulation by Perivascular Adipose Tissues
Published on: June 3, 2019
 10:28
Evaluation of Vascular Control Mechanisms Utilizing Video Microscopy of Isolated Resistance Arteries of Rats
Published on: December 5, 2017
Related Concept Videos
 01:26
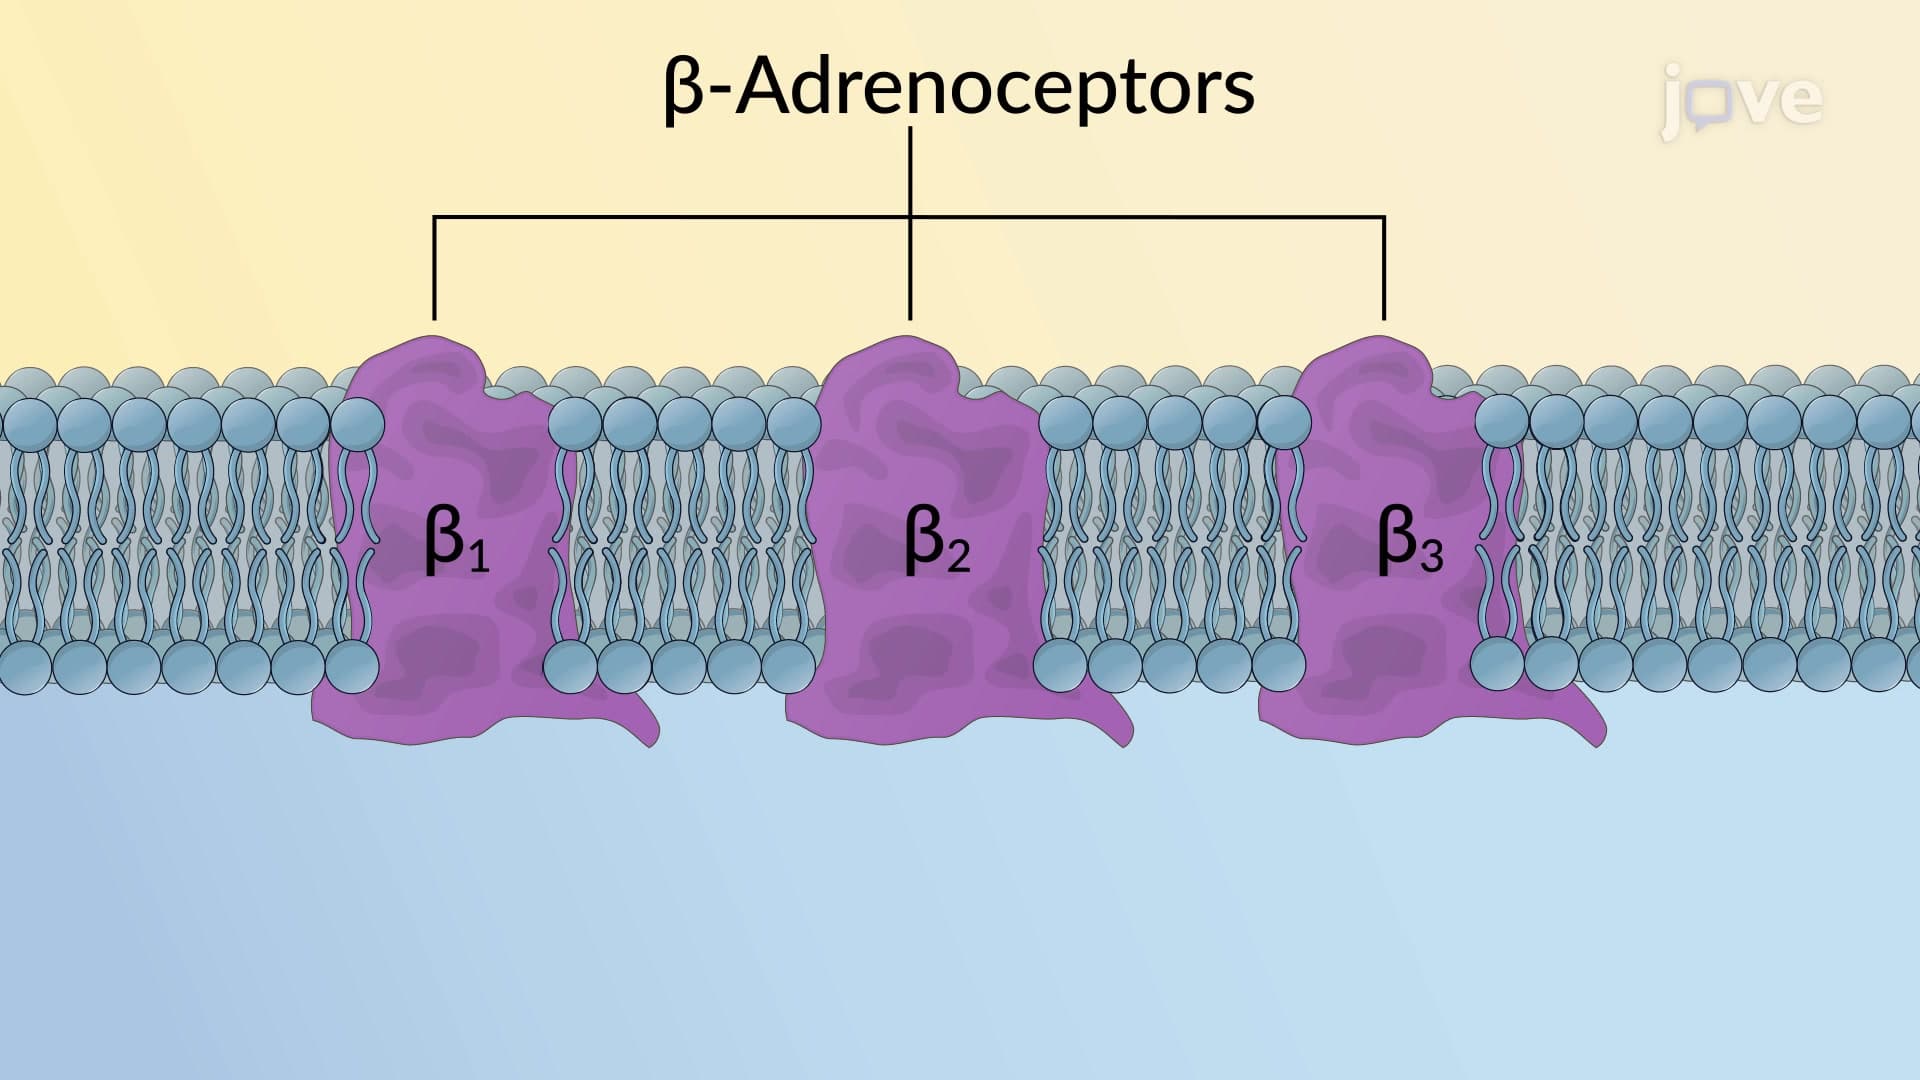
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:17
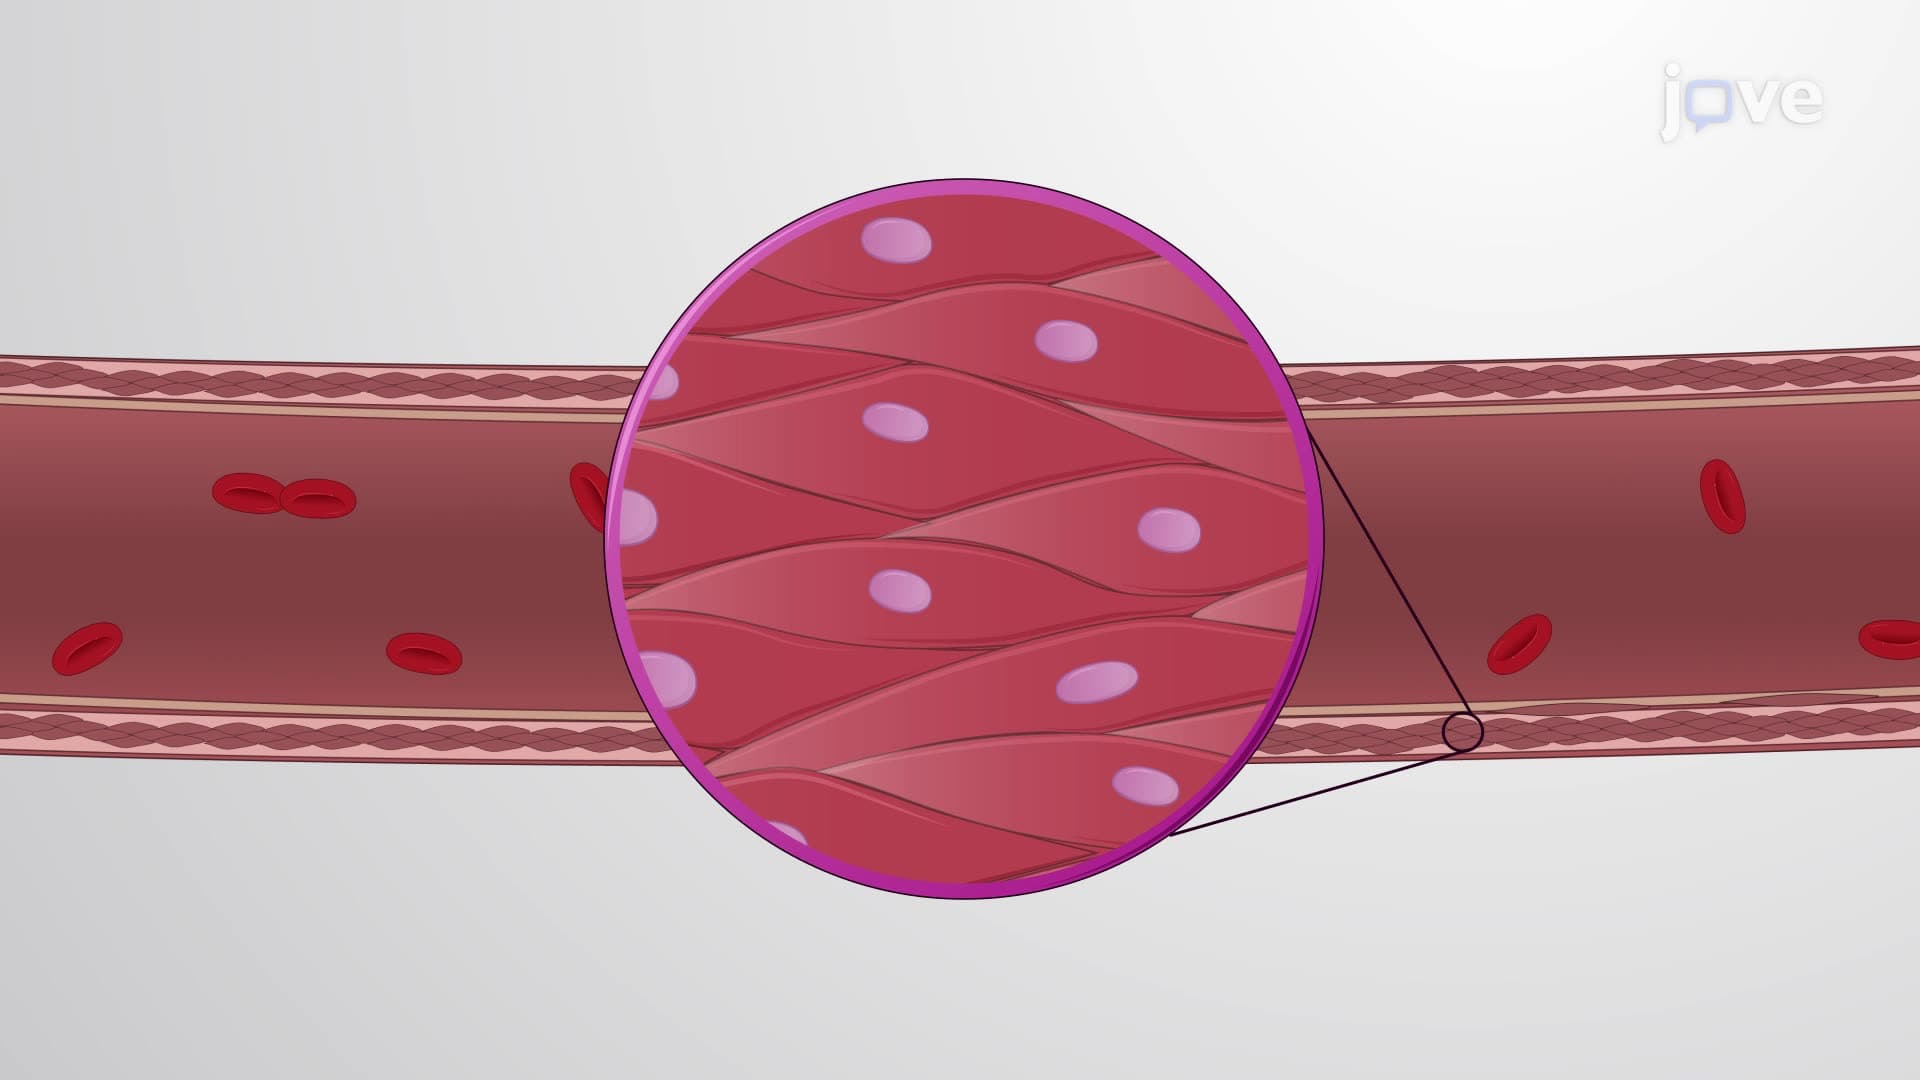
Autoregulation of Blood Flow
Chemical Signaling in Autoregulation
Chemical signaling operates at the precapillary sphincter level, inciting either contraction or relaxation.
 01:31
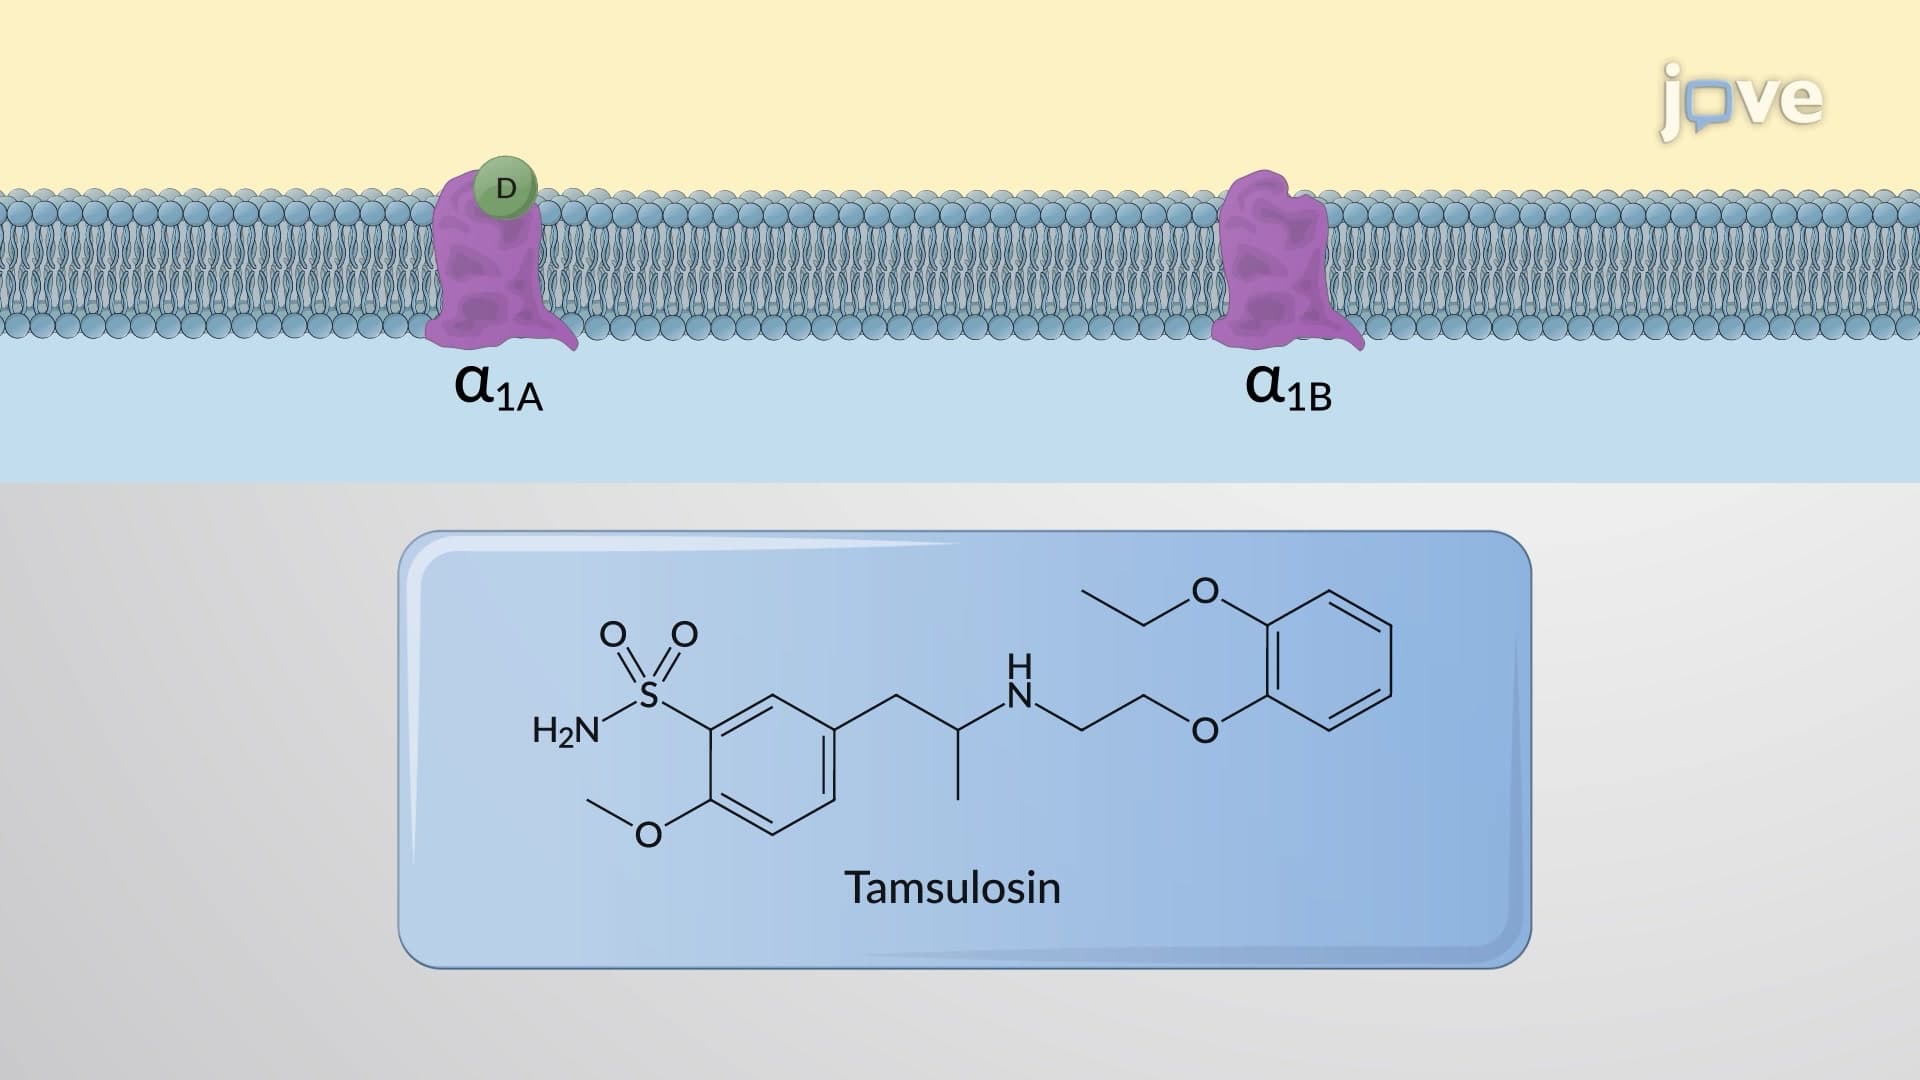
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:23
Antihypertensive Drugs: Vasodilators
 01:18
Antihypertensive Drugs: Action of Calcium Channel Blockers