Concurrent chemoradiotherapy followed by metastasectomy converts to survival benefit in stage IV rectum cancer
Related Experiment Video
Updated: May 20, 2026
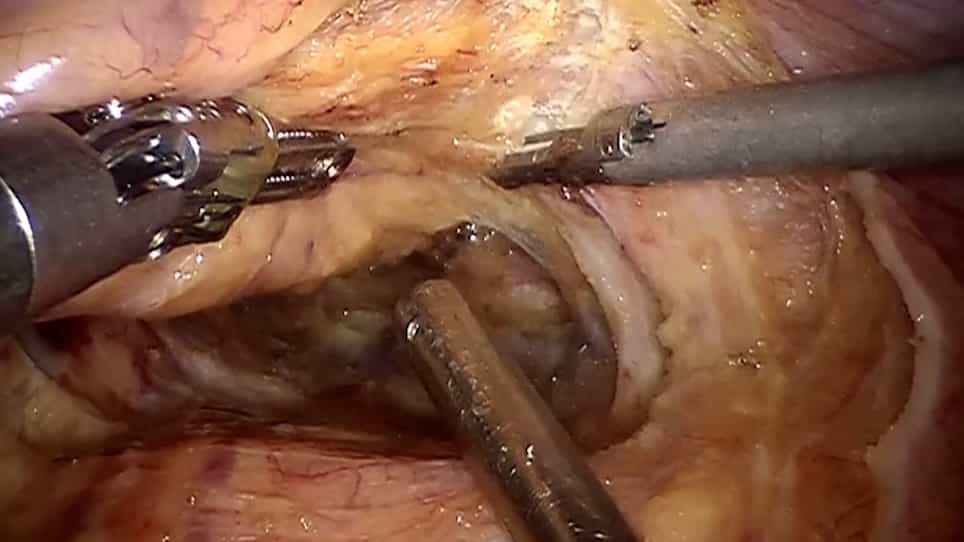
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Jen-Kou Lin1, Lin-Kun Lee, Wei-Shone Chen
1School of Medicine, National Yang-Ming University, Taipei, Taiwan.

Background:
To investigate the impact of concurrent chemoradiotherapy (CCRT) on stage IV rectum cancer.
Methods:
Between 2000 and 2011, 297 consecutive patients diagnosed with stage IV rectum cancer (synchronous metastasis) were enrolled. Cox proportional hazard analyses were used for prognostic factors determination, and the Kaplan-Meier method was used for survival analyses. Propensity scores with the one-to-one nearest-neighbor matching model were used to select matched patients for validation studies.
Results:
In total, 63 patients received CCRT and 234 did not. The patients in the CCRT group were younger, had more low-lying lesions, and had more T4 lesions, lung metastases, metastasectomies, and oxaliplatin-based upfront chemotherapy. Before propensity-score matching, a younger age (HR = 0.662, P = 0.016), lower carcinoembryonic antigen (CEA) level (≤20 ng/ml) (HR = 0.531, P = 0.001), no metastasectomy (HR = 3.214, P < 0.001), and no CCRT (HR = 1.844, P = 0.019) were independent prognostic factors after controlling for other confounding factors. After matching, only CEA and metastasectomy, but not CCRT, were independent prognostic factors. The survival benefit of CCRT was restricted to patients who undergo subsequent metastasectomy.
Conclusions:
Upfront CCRT only provided a survival benefit in patients with stage IV rectum cancer who undergo subsequent metastasectomy.
