Related Experiment Video
Updated: Apr 26, 2026

Author Spotlight: Unveiling the Therapeutic Effects of FSN Treatment – Bridging Research and Clinical Applications in Neuropathic Pain
Published on: June 30, 2023
Botulinum toxin for myofascial pain syndromes in adults
Adriana Soares1, Régis B Andriolo, Alvaro N Atallah
1Department of Medicine, Universidade Federal de São Paulo, Rua Grão Pará, 570 apt.1101 Bairro Santa Efigênia, Belo Horizonte, Minais Gerais, Brazil, 30150-341.

Background:
This is an updated version of the original Cochrane review published in Issue 4, 2012. Myofascial pain syndrome (MPS) is a regional muscular pain syndrome characterised by the presence of trigger points, which are painful points in one or more muscles. The pain can be felt at the site where the trigger point is located or it can be felt away from that place when the muscle is pressed (referred pain). Botulinum toxin is a protein produced by the bacterium Clostridium botulinum and is a potent neurotoxin that eventually inhibits muscle contractions. It is capable of selectively weakening painful muscles and interrupting the pain cycle.
Objectives:
To assess the effectiveness and safety of botulinum toxin A (BTXA) in the treatment of myofascial pain syndrome (MPS), excluding MPS in neck and head muscles.
Search Methods:
This is an updated version of the original Cochrane review published in Issue 4, 2012. The search strategy for the update was the same as in the original review and we searched CENTRAL in The Cochrane Library (2013, Issue 11 of 12), MEDLINE (Ovid) (2012 to 29 November 2013) and EMBASE (Ovid) (2012 to 27 November 2013). The search strategy was composed of terms for myofascial pain and botulinum toxin. For the original review, we also searched the Cochrane Pain, Palliative and Supportive Care (PaPaS) Review Group Specialised Register until December 2011, PubMed (from 1966 to 2011) and LILACS (from 1982 to 2011). There was no language restriction.
Selection Criteria:
We included randomised controlled trials (RCTs) involving botulinum toxin for treating participants with MPS. We excluded studies with MPS of the neck and head from this review as they have already been assessed in existing systematic reviews. We considered a diagnosis of MPS to be based on the identification of trigger points in the taut band through palpation of sensitive nodules, local twitch response and specific patterns of referred pain associated with each trigger point.
Data Collection And Analysis:
Two review authors independently screened identified studies, extracted data, assessed trial quality and analysed results using the Cochrane PaPaS Review Group criteria.
Main Results:
Four studies with a total of 233 participants, comparing BTXA with placebo, met the inclusion criteria. In one study with 145 participants, significant improvement rates of pain intensity scores and duration of daily pain were demonstrated when comparing BTXA with placebo. The three other studies showed that there was no statistically significant difference between BTXA and placebo in pain intensity.
Authors' Conclusions:
Since the first publication of this review, no new studies were found. There is inconclusive evidence to support the use of botulinum toxin in the treatment of MPS based on data from four studies with a total of 233 participants, which we considered were of sufficient quality to be included in this review. Meta-analyses were not possible due to the heterogeneity between studies. We suggest that in future studies the same methodology to assess pain, a standardised dose of treatment, follow-up of at least four months (to observe the maximum and minimum curve of the drug effect) and appropriate data presentation should be used. More high-quality RCTs of botulinum toxin for treating MPS need to be conducted before firm conclusions on its effectiveness and safety can be drawn.
Related Concept Videos
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:20
Myasthenia Gravis: Overview and Treatment
These antibodies interfere with the function of the nicotinic receptors in three ways: by binding to the receptor and disrupting acetylcholine binding; by causing cross-linking of receptors which...
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...
 01:24
Centrally Acting Muscle Relaxants: Therapeutic Uses
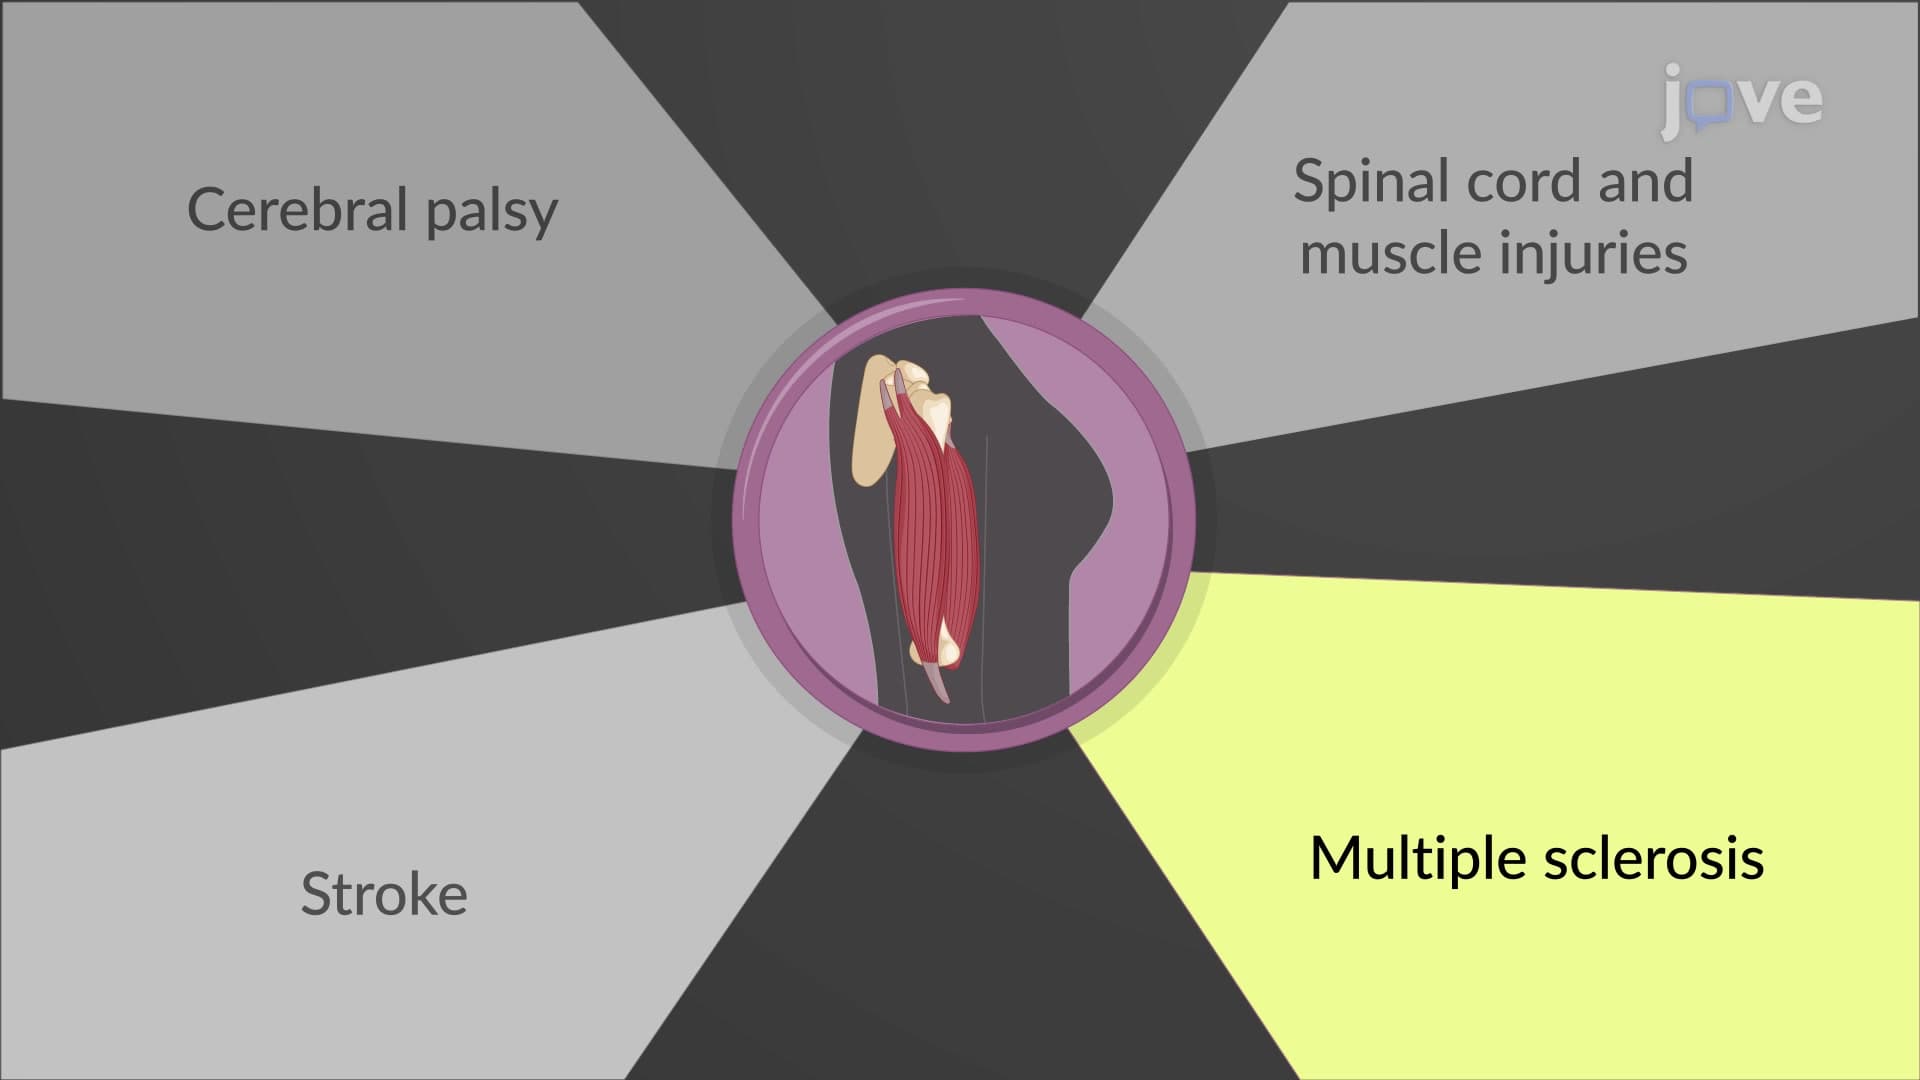
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...