Renal tubular acidosis complicated with hyponatremia due to cortisol insufficiency
Related Experiment Video
Updated: Mar 29, 2026
A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Yuichiro Izumi1, Yushi Nakayama1, Tomoaki Onoue1
1Department of Nephrology , Kumamoto University Graduate School of Medical Sciences , Kumamoto, Kumamoto , Japan.

Abstract:
Adrenocortical insufficiency such as occurs in Addison's disease causes hyponatremia and renal tubular acidosis (RTA). Hyponatremia results from both aldosterone and cortisol insufficiency. RTA is due to aldosterone insufficiency. The involvement of cortisol in RTA is unclear. Here, we report a woman in her 70s who was admitted to our hospital with severe hyponatremia (106 mEq/l) and RTA. The patient exhibited low plasma cortisol levels with little response to rapid adrenocorticotropic hormone loading. In contrast, the plasma aldosterone concentration was maintained at or above the normal range. Hydrocortisone replacement greatly improved both the hyponatremia and RTA. This case suggests that both aldosterone and cortisol are involved in acid secretion from the kidney.

Related Concept Videos
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:29
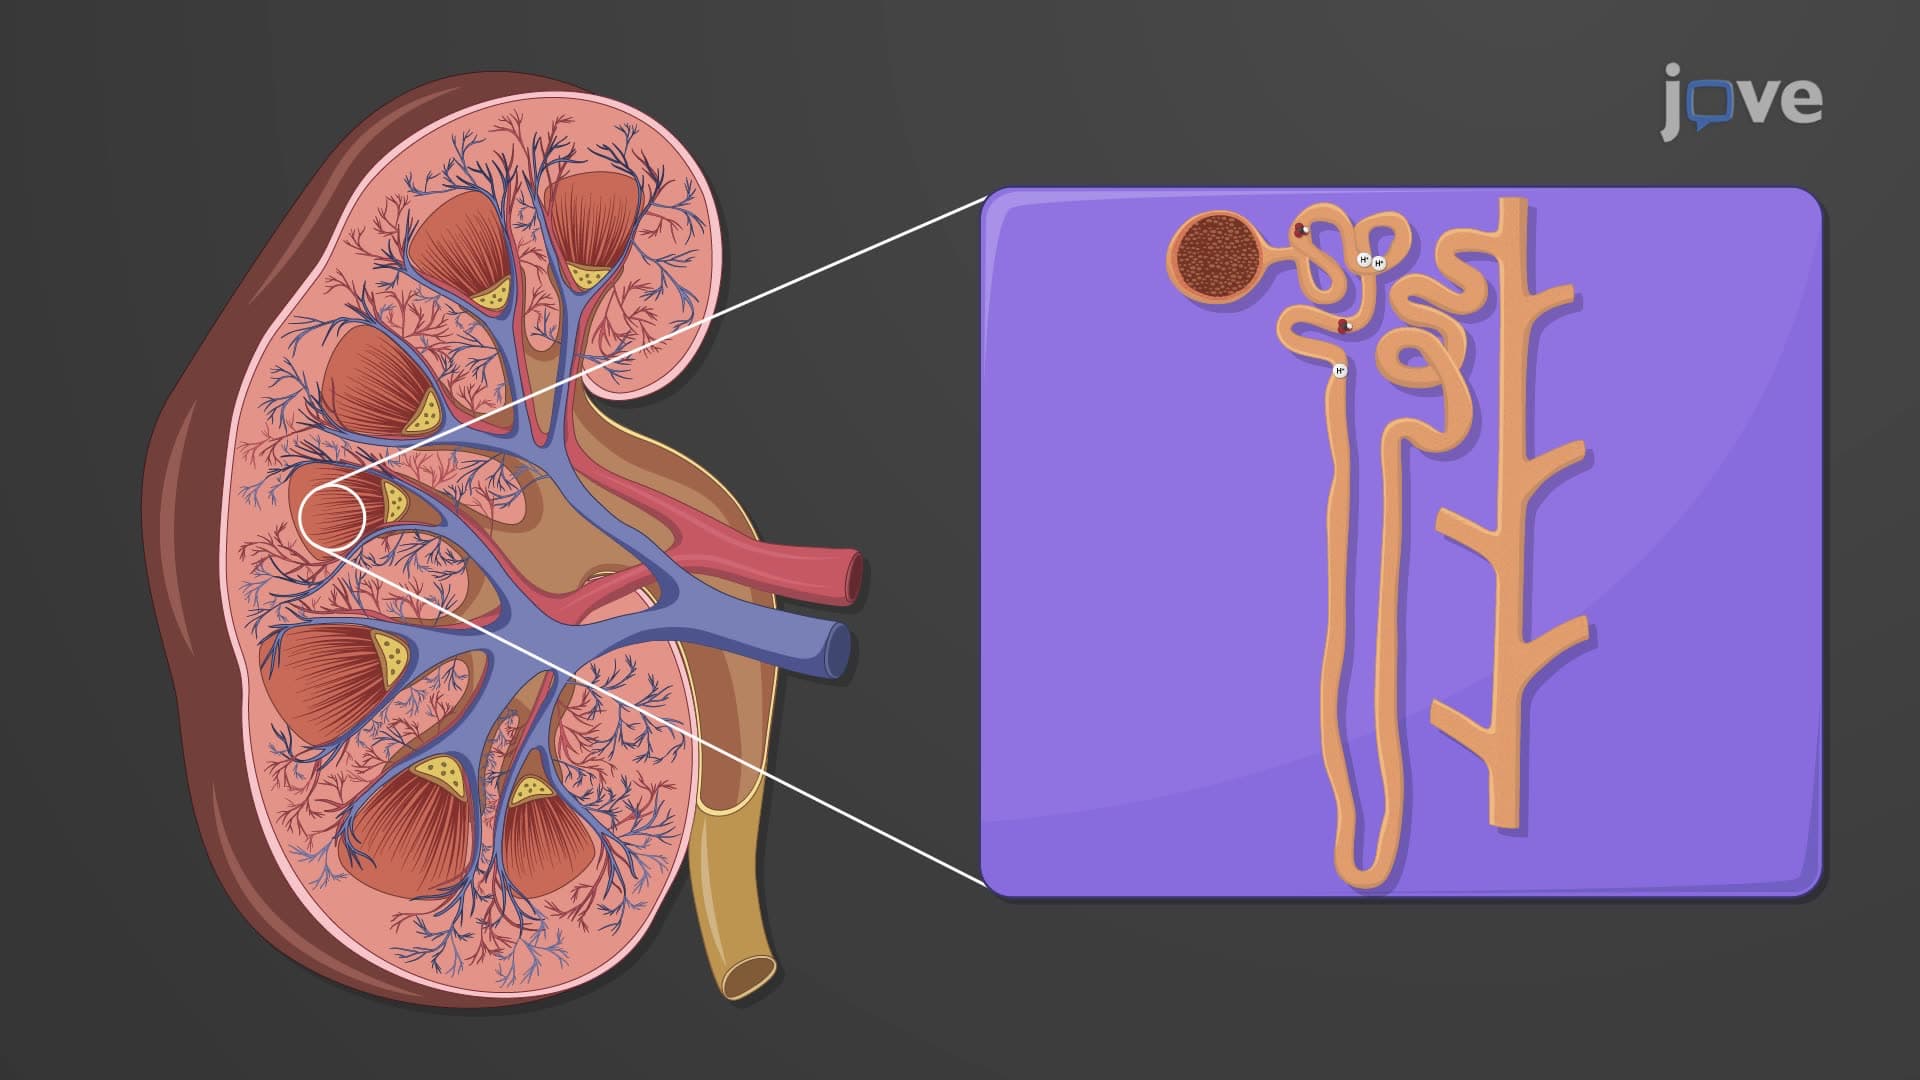
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:22
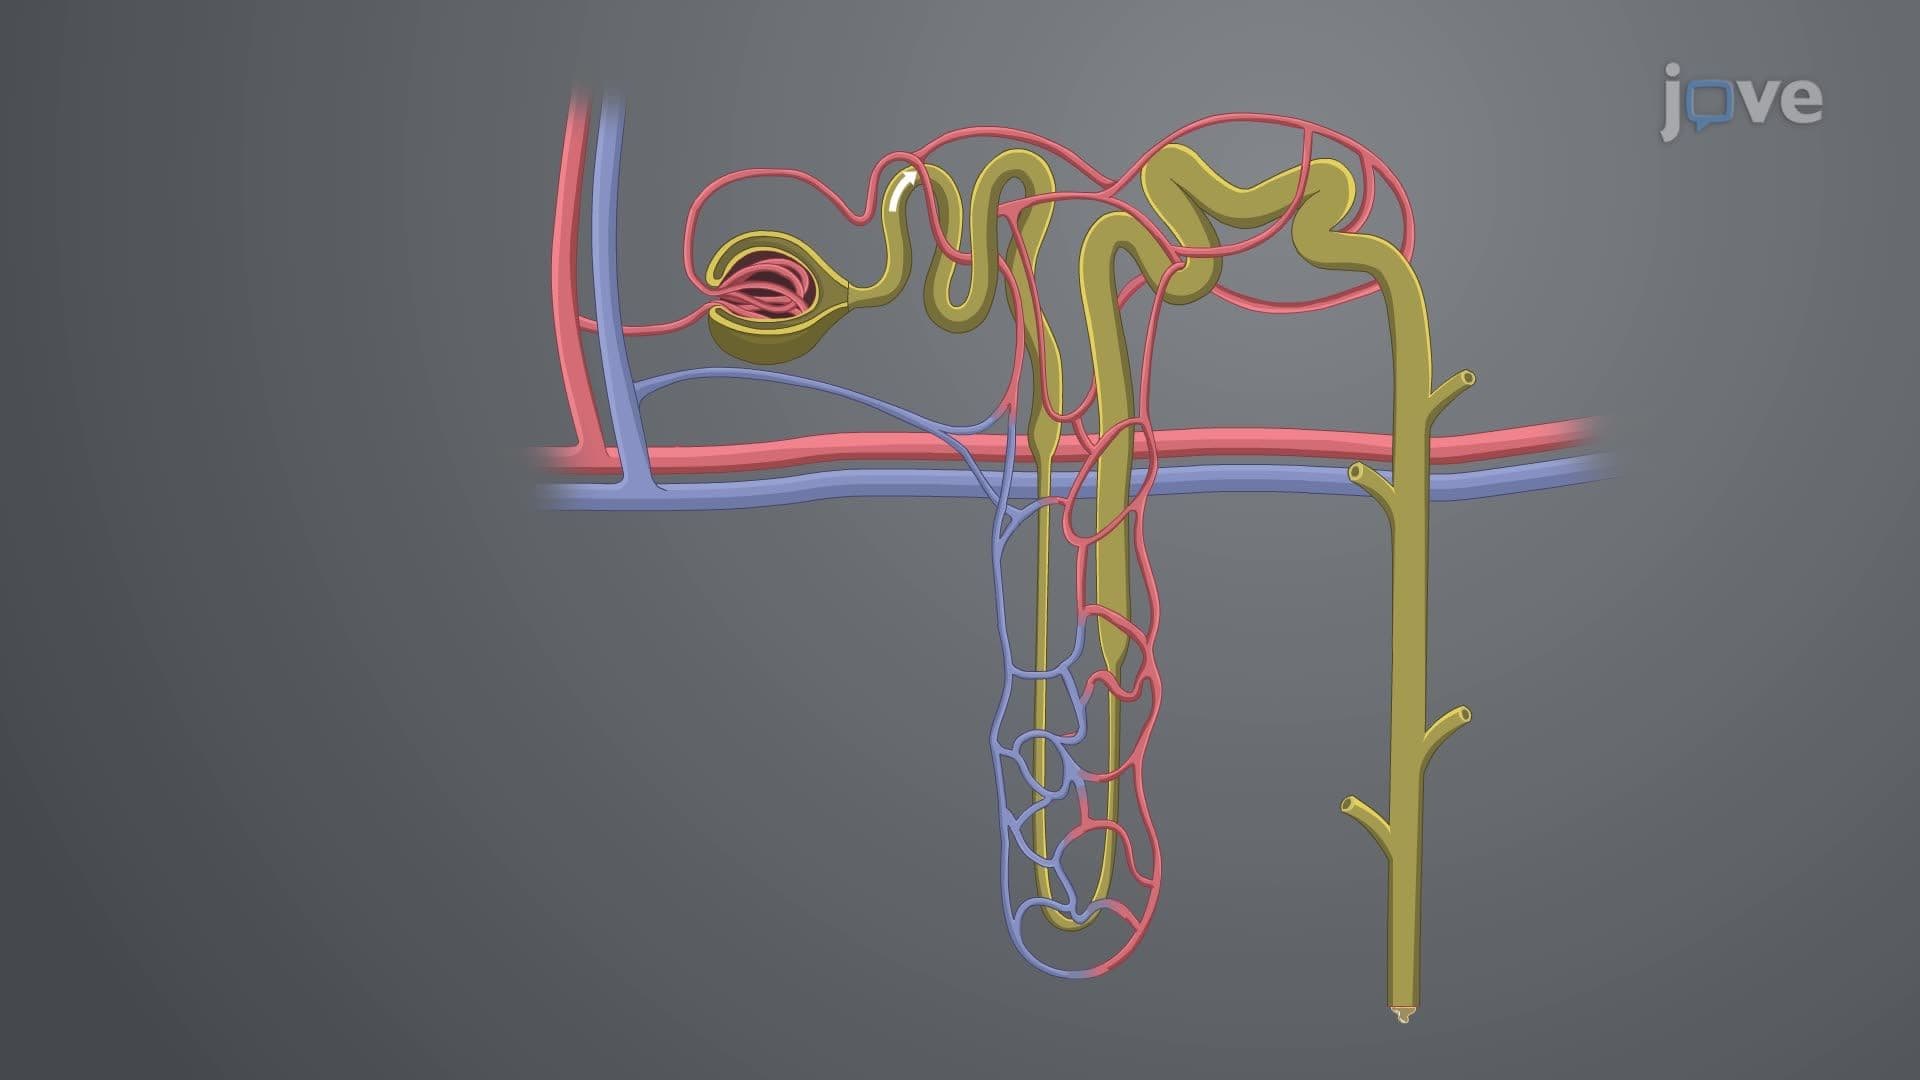
Physiology of the Genitourinary System II: Tubular Reabsorption and Secretion
 01:29
Acute Kidney Injury II: Pathophysiology
 01:22
Acute Kidney Injury VI: Nursing Management
 01:29
Acute Kidney Injury III: Clinical Manifestations