American Thyroid Association Scientific Statement on the Use of Potassium Iodide Ingestion in a Nuclear Emergency

Angela M Leung1,2, Andrew J Bauer3,4, Salvatore Benvenga5,6

  • 11 Division of Endocrinology, Diabetes, and Metabolism, Department of Medicine, UCLA David Geffen School of Medicine , Los Angeles, California.

Related Concept Videos

Synthesis and Regulation of Thyroid Hormones01:20

Synthesis and Regulation of Thyroid Hormones

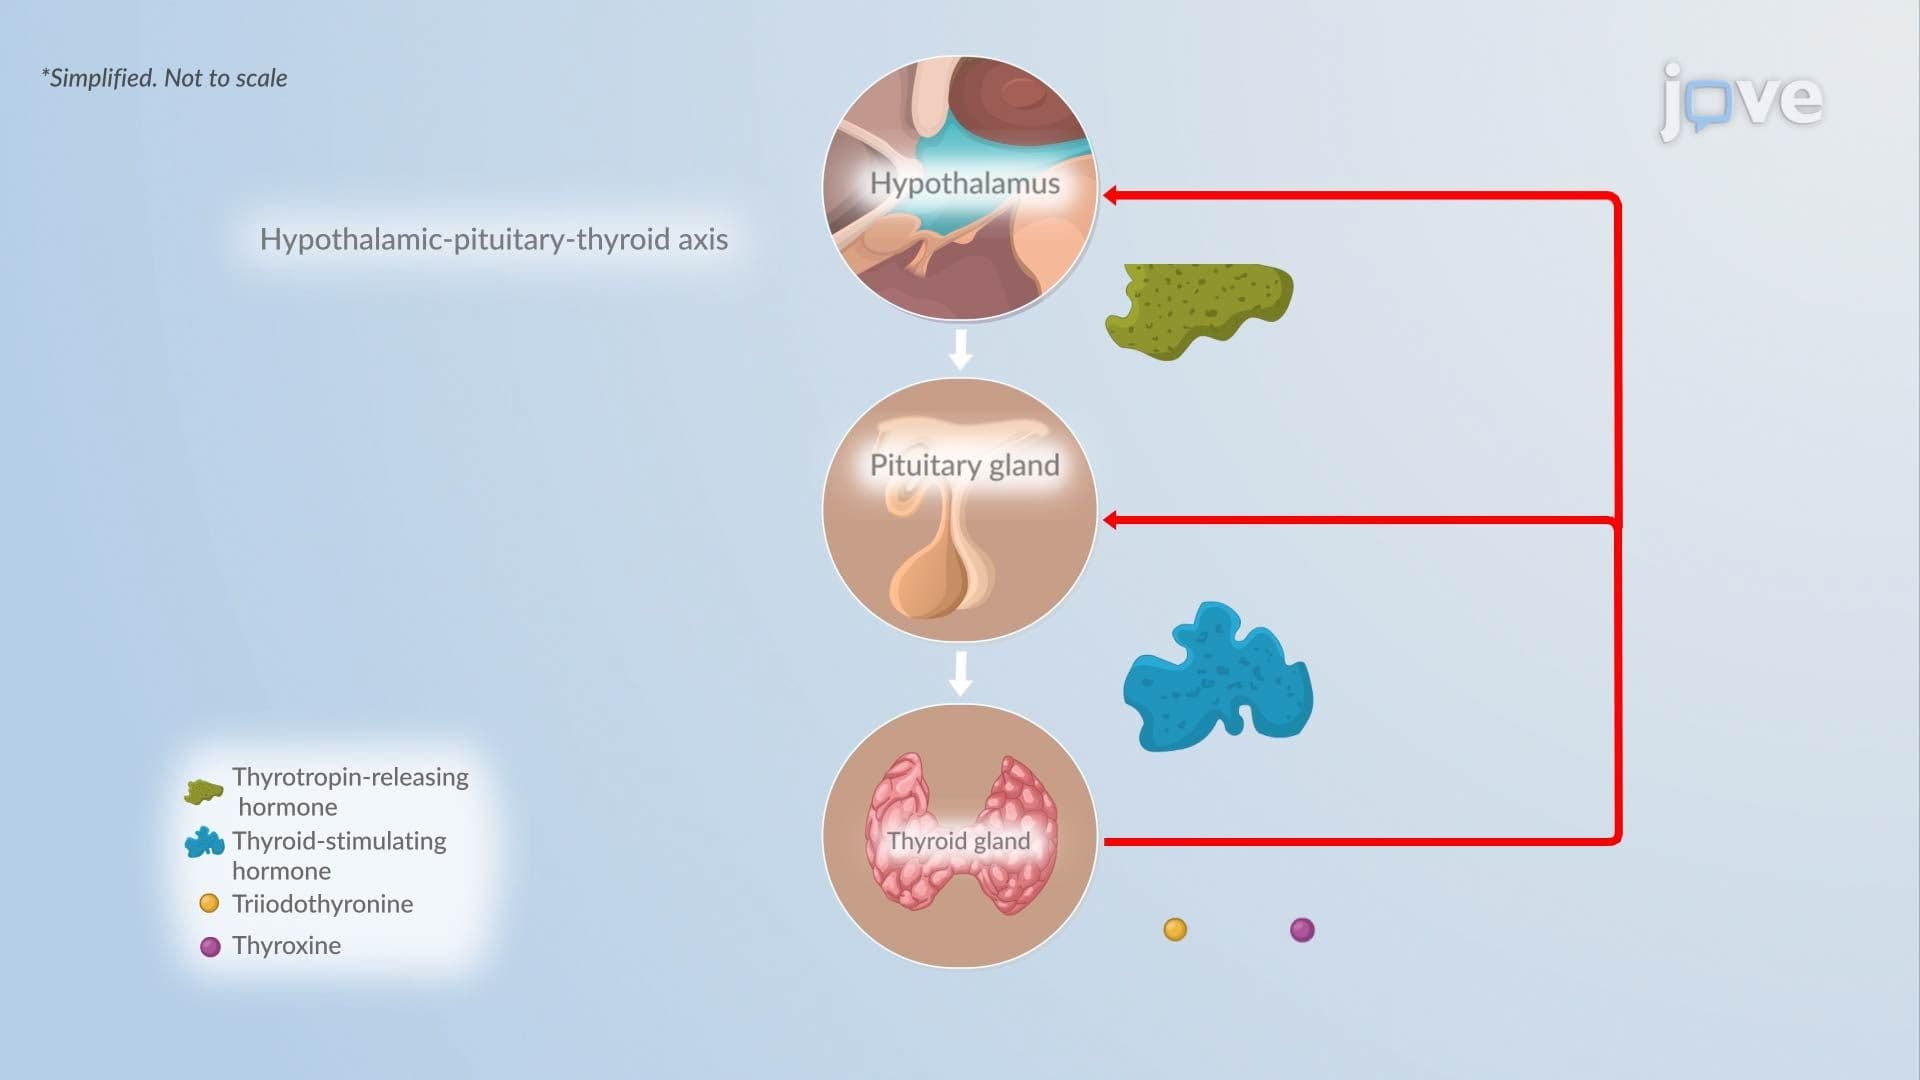
Low blood levels of the thyroid hormones — triiodothyronine (T3) and thyroxine (T4) — signal the hypothalamus to release the thyrotropin-releasing hormone (TRH). TRH then reaches the pituitary gland and stimulates the release of thyroid-stimulating hormone(TSH) into the bloodstream.
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers01:12

Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers

Class III antiarrhythmic drugs are a group of medications that can prolong action potentials in the heart. They achieve this by blocking potassium channels or enhancing inward currents from sodium channels. However, these drugs have a unique property of "reverse use-dependence," which is most pronounced at slower heart rates and can lead to torsades de pointes—a specific type of arrhythmia. However, it is essential to note that excessive QT interval prolongation—a measure of the heart's...
Acute Kidney Injury IV: Diagnostic Studies and Prevention01:30

Acute Kidney Injury IV: Diagnostic Studies and Prevention
Accurate diagnosis and effective prevention are critical in managing Acute Kidney Injury (AKI), which is linked to high mortality rates ranging from 10% to 80%. Timely recognition of at-risk patients and careful monitoring can significantly reduce the likelihood of kidney damage.Diagnostic Assessments:The diagnostic process starts with a comprehensive medical history to identify prerenal, intrarenal, and postrenal causes.Prerenal causes, such as dehydration, hypotension, or blood loss, should...
Hyperthyroidism I: Introduction01:25

Hyperthyroidism I: Introduction

Hyperthyroidism is a type of thyrotoxicosis characterized by the thyroid gland's overproduction of the thyroid hormones triiodothyronine (T3) and thyroxine (T4). This hormone excess increases the basal metabolic rate and enhances sensitivity to catecholamines.DiagnosisDiagnosis is based on clinical features and biochemical testing. It typically shows suppressed thyroid-stimulating hormone (TSH) levels below 0.4 mIU/L, with elevated free T3 and/or T4. Additional tests, including thyroid...
Hyperthyroidism II: Pathophysiology01:27

Hyperthyroidism II: Pathophysiology

Hyperthyroidism is a hypermetabolic state caused by elevated levels of thyroid hormones, triiodothyronine (T3) and thyroxine (T4). It results from dysregulation at the thyroid, pituitary, or immune system level and affects multiple organ systems.PathophysiologyThe most common cause of hyperthyroidism is Graves’ disease, an autoimmune disorder in which antibodies, specifically thyroid-stimulating antibodies (TSAb), a subtype of TSH receptor antibodies (TRAb), bind to and activate TSH receptors...
Goiter01:27

Goiter

Goiter refers to an abnormal enlargement of the thyroid gland that may appear as a diffuse goiter (uniform enlargement) or nodular (single or multiple nodules). Functionally, it is classified as nontoxic (normal/low hormone levels) or toxic (excess hormone production).PathophysiologyDiffuse thyroid enlargement typically results from prolonged stimulation by thyroid-stimulating hormone (TSH) or TSH-like agents, commonly seen in hypothyroidism or iodine deficiency. In contrast, in hyperthyroid...