Related Experiment Video
Updated: Jan 25, 2026


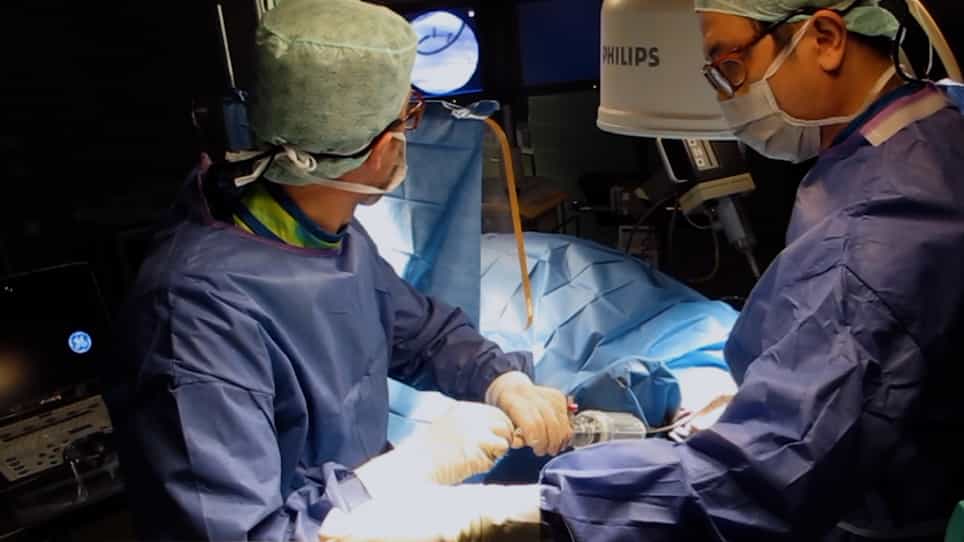
Implantation of Total Artificial Heart in Congenital Heart Disease
Published on: July 18, 2014
Workforce Cost Model for Expanding Congenital and Rheumatic Heart Disease Services in Kenya
Nelly-Ange T Kontchou1, Andrew W McCrary2, Kevin A Schulman3
11 Harvard Medical School, Boston, MA, USA.

Insights
Scaling cardiac care in low- and middle-income countries (LMICs) requires understanding workforce needs. This study models the cost and staffing for cardiovascular services in Kenya, offering a framework for LMIC capacity building.
Area of Science:
- Global Health
- Cardiovascular Medicine
- Health Workforce Planning
Background:
- Cardiovascular disease (CVD) is the leading global cause of death, disproportionately affecting low- and middle-income countries (LMICs).
- Effective CVD management in LMICs necessitates robust medical and surgical services.
- This study focuses on Kenya as a model for scaling cardiac care in LMICs.
Purpose of the Study:
- To model the workforce needs and associated costs for cardiovascular services in Kenya.
- To provide an adaptable framework for other LMICs to assess and scale their cardiac provider workforce.
Main Methods:
- A model was developed using epidemiological data from sub-Saharan Africa to estimate disease burden (congenital and rheumatic heart disease) in a simulated 1,000-person population.
- Services modeled included clinic visits, echocardiograms, cardiac catheterizations (diagnostic and interventional), and heart surgery.
- Costs were based on Kenyan public sector salaries, with sensitivity analyses performed on service duration and salaries.
Main Results:
- An estimated 2.5 heart surgeries per 1,000 people annually are needed, costing US$526.
- Total annual workforce cost for comprehensive cardiac services (including clinic visits, echocardiograms, and catheterizations) is US$899 per 1,000 people.
- Kenya requires an estimated 196 full-time equivalent cardiac surgeons for its population, based on 2017 figures and public sector workforce productivity.
Conclusions:
- A scalable model for cardiovascular service staffing, based on disease burden and workforce costs, has been presented.
- This model facilitates local capacity building for essential cardiac care in LMICs.
Background:
Cardiovascular disease is the number one global killer, with over three quarters of these deaths arising from the populations of low- and middle-income countries (LMICs). Addressing the burden of cardiovascular disease in LMICs must include medical and surgical services for these patients. In this article, we model the needs and costs to scale up the cardiac provider workforce in Kenya, which can be adapted to other LMICs based on country-specific workforce hours and workforce salaries.
Methods:
Using published epidemiological reports from sub-Saharan Africa, we structured the model based on the expected disease burden of congenital and rheumatic disease in a simulated 1,000-person population. Services modeled include clinic visits, echocardiograms, diagnostic cardiac catheterizations, interventional catheterizations, and heart surgery. Costs were modeled based on Kenyan public sector salaries. After scaling the model, we created a sensitivity analysis of change in service duration and salaries.
Results:
Based on a 1,000-person Kenyan population, we estimate that 2.5 heart surgeries will be needed every year, with a corresponding annual workforce cost of US$526. Including accompanying services of clinic visits, echocardiograms, and both diagnostic and interventional cardiac catheterizations, the total annual workforce cost is US$899. Based on estimated productive hours for public sector workforce, 196 full-time equivalent cardiac surgeons will be needed for the entire population of Kenya (2017 figure).
Conclusions:
We present a model for appropriate cardiovascular service staffing based on disease burden and workforce costs. This model can be scaled up as needed to plan for local capacity building.
More Related Videos
 05:31
Transcatheter Pulmonary Valve Replacement from Autologous Pericardium with a Self-Expandable Nitinol Stent in an Adult Sheep Model
Published on: June 8, 2022
 08:28
Analysis of Congenital Heart Defects in Mouse Embryos Using Qualitative and Quantitative Histological Methods
Published on: March 10, 2020
Related Concept Videos
 01:23
Rheumatic Heart Disease I: Introduction
 01:20
Rheumatic Heart Disease IV: Nursing Management
 01:21
Rheumatic Heart Disease III: Medical Management
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and...
 01:30
Primary Healthcare Services
In 1978, international leaders convened in Alma-Ata, Kazakhstan, for what would be a pivotal event in global health. The Alma-Ata Declaration was the first to call...