Related Experiment Video
Updated: Dec 13, 2025


A Novel Rescue Technique for Difficult Intubation and Difficult Ventilation
Published on: January 17, 2011
Neurally-Adjusted Ventilatory Assist Can Facilitate Extubation in Neonates With Congenital Diaphragmatic Hernia
Ryan D Meinen1, Yousef I Alali2, Awni Al-Subu3
1Division of Neonatology, University of Wisconsin-Madison, Madison, Wisconsin.

Background:
Congenital diaphragmatic hernia is associated with a high risk of neonatal mortality and long-term morbidity due to lung hypoplasia, pulmonary hypertension, and prolonged exposure to positive-pressure ventilation. Ventilator-associated lung injury may be reduced by using approaches that facilitate the transition from invasive ventilation to noninvasive ventilation (NIV), such as with neurally-adjusted ventilatory assist (NAVA). We reported our use of NAVA in neonatal patients with congenital diaphragmatic hernia during the transition from invasive ventilation to NIV.
Methods:
A retrospective analysis of neonatal subjects with congenital diaphragmatic hernia admitted to a tertiary care children's hospital between December 2015 and May 2018 was conducted. Subject data and factors that affected the use of NAVA were analyzed.
Results:
Ten neonatal subjects with congenital diaphragmatic hernia were placed on NAVA, and 6 were successfully transitioned, after surgery, from pressure control synchronized intermittent mandatory ventilation to invasive ventilation with NAVA and then to NIV with NAVA without the need for re-intubation. The transition from pressure control synchronized intermittent mandatory ventilation to invasive ventilation with NAVA resulted in a decrease in peak inspiratory pressure, mean airway pressure, and [Formula: see text]. Barriers to the use of NAVA included symptomatic pleural effusion or chylothorax and pulmonary sequestration.
Conclusions:
Both invasive ventilation with NAVA and NIV with NAVA were used successfully in subjects with congenital diaphragmatic hernia during the transition from invasive ventilation to NIV. The transition to NAVA was associated with a decrease in peak inspiratory pressure, mean airway pressure, and the need for supplemental oxygen. A prospective trial is needed to determine the short- and long-term impacts of this mode of ventilation in neonates with congenital diaphragmatic hernia.

Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:14
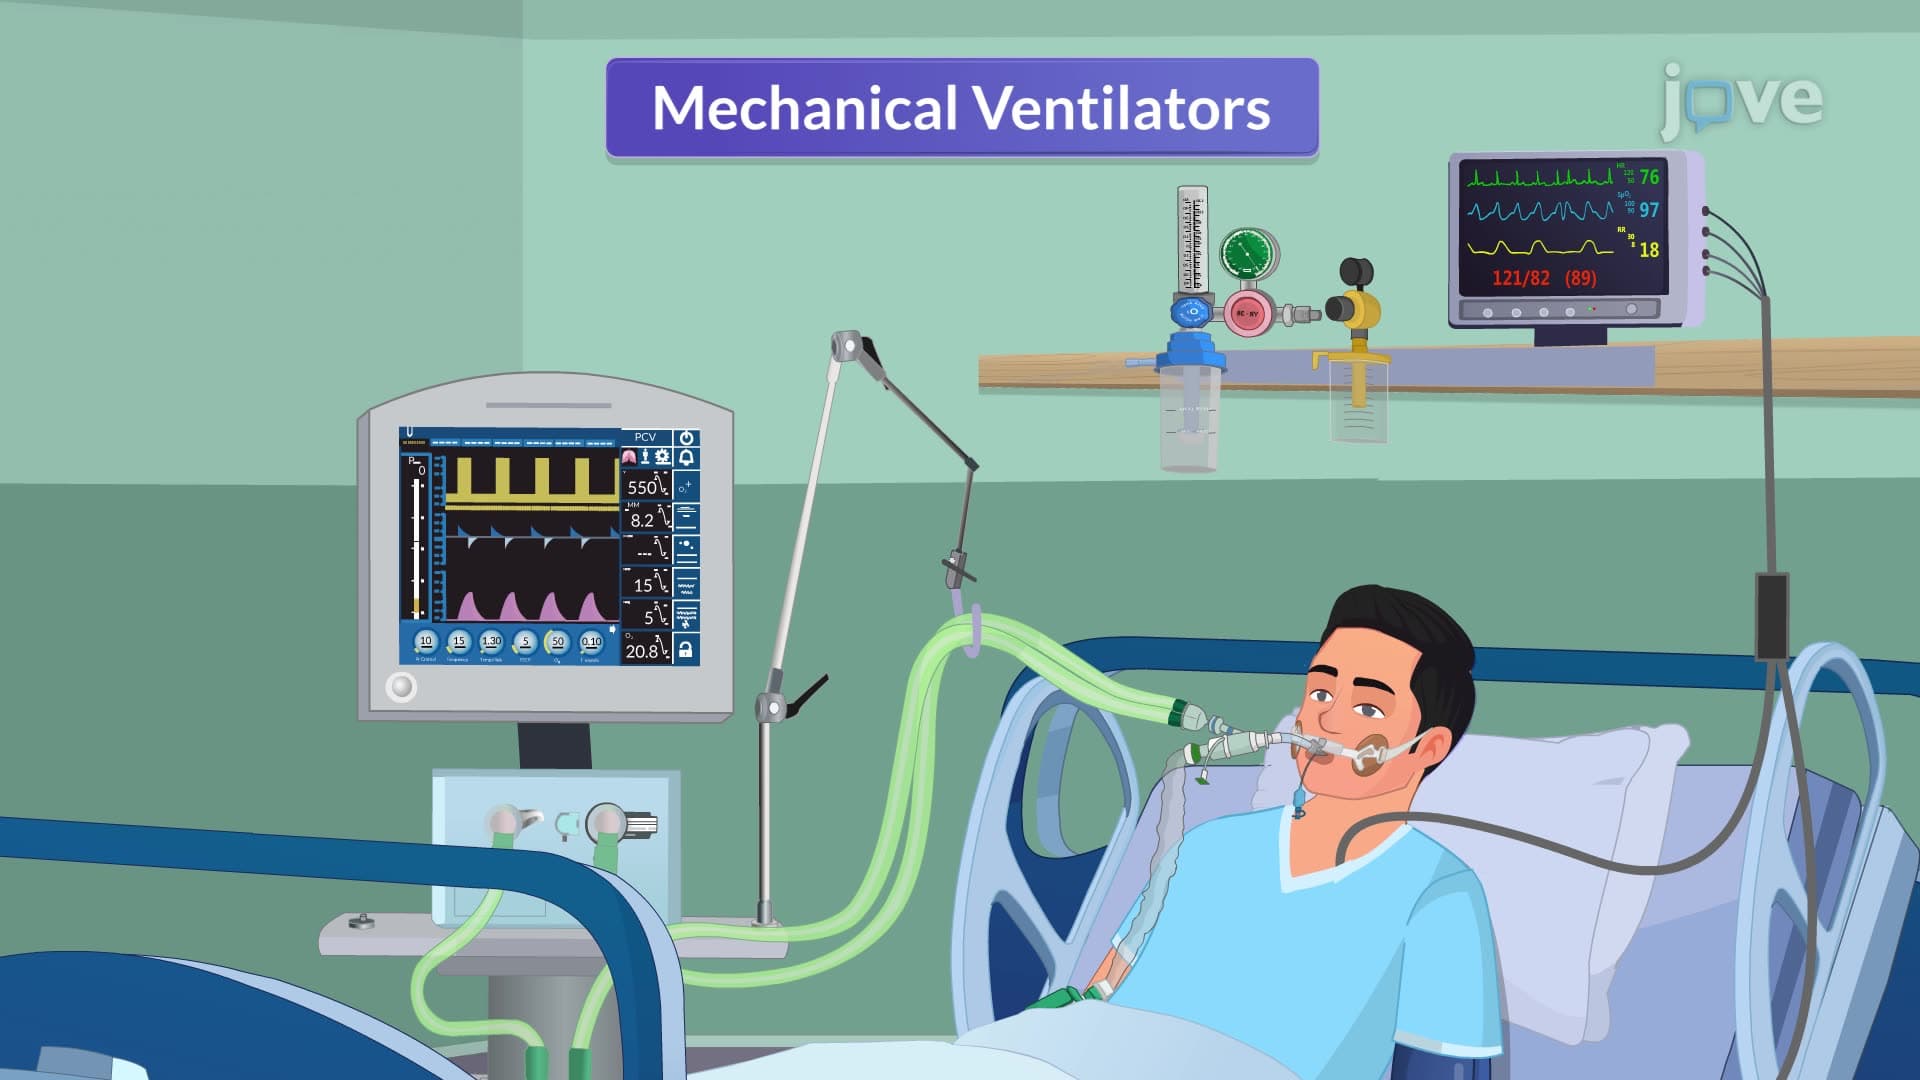
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:29
Mechanical Ventilation I: Indication and Settings
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...