Related Experiment Video
Updated: Dec 8, 2025
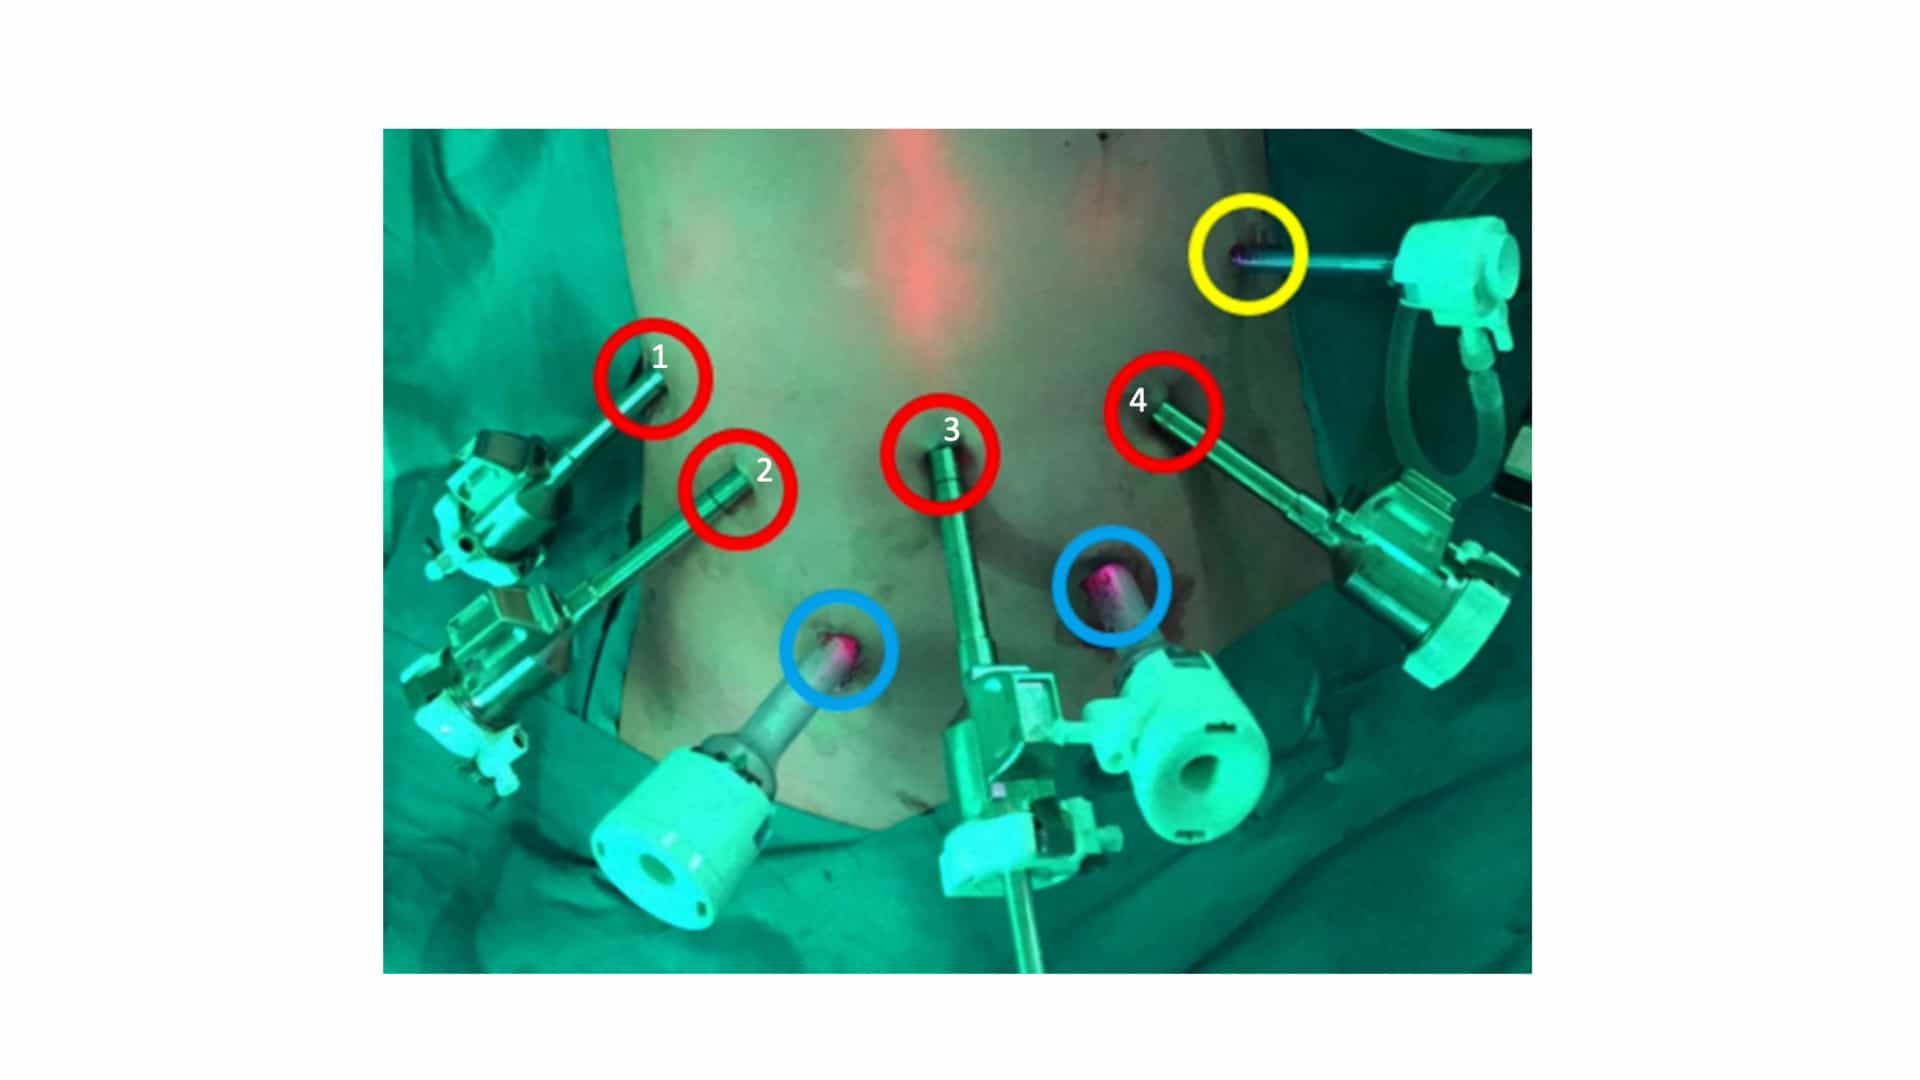

Robotic D3 Partial Duodenal Resection with Primary Side-to-Side Anastomosis
Published on: December 15, 2023
; RESULTS OF RESECTION METHODS OF TREATMENT IN PATIENTS WITH GIANT PYLORODUODENAL ULCERS COMPLICATED BY PERFORATION
A Kosenkov1, E Stoliarchuk1, E Belykh1
11Sechenov First Moscow State Medical University, Moscow, Russian Federation.

Abstract:
We studied the immediate and long-term results of various methods of gastric resection in 35 patients operated at the S.S. Yudin State Medical Center in Moscow from 2000 to 2019. 20 (57.1%) patients were operated on for perforation, and 15 (42.6%) patients underwent surgery for ulcerative bleeding. There were 27 (77.2%) males and 8 (22.8%) females. The average age of patients was 48.3±2.3 years. The diagnosis of peptic ulcer disease was previously made in 24 (68.6%) patients, the duration of the disease was 7.7±2.7 years. Of the 35 patients, 29 (82.8%) underwent standard gastric resection without vagotomy with Billroth-II anastomosis in various modifications and 6 (17.2%) underwent pylorobulbar resection with Billroth-I anastomosis with bilateral stem vagotomy. According to the analysis of the results of surgical interventions, gastric resection was accompanied by a significant number of early postoperative complications observed in 18 (51.4% of patients): associated with the nature of the operation, 10 and 5 patients had complications from the cardiovascular and respiratory systems. The most frequent complication due to the nature of surgery was a clinically significant violation of the evacuation function of the stomach stump, which developed in 8 of 35 (22.8%) patients. In 4 patients after pylorobulbar resection, the violation of the evacuation function of the stump was due to its parasympathetic denervation. The remaining 4 patients after standard resection of gastric stasis stump occurred due to maintenance of anastomositis of gastrojejunal anastomosis. Post-vagotomic diarrhea: observed in 3 of 6 patients: 1 patient of moderate severity, and 2 patients-mild. Failure of sutures was observed in 2 out of 35 (5.7%) patients after standard gastric resection: one after resection of Hofmeister Finsterer and the other after resection for PY. Complications from the cardiovascular system were observed in 5 (14.3%) patients. After surgery, 5 (22.7%) patients died: 4 after resection of 2/3 of the stomach and 1 patient after pyloroduodenal resection with stem vagotomy. All the deceased were operated on urgently: 2 patients for perforation of giant ulcers and 3 patients for continuing profuse bleeding. The causes of death of patients operated on for bleeding were: myocardial infarction in 1 patient, pulmonary embolism in 2 patients. Another 2 patients with failure of duodenal stump sutures, operated on for perforation of giant ulcers, died from increasing cardiovascular insufficiency. The analysis of long-term results of surgical interventions showed a steady decrease in the number of post gastric resection and post-vagotomic disorders, as well as the absence of ulcer recurrence. It should be noted that the phenomena of dumping syndrome observed in patients after standard gastric resection were not severe and were corrected by a lax diet. After piloroduodenal resection with anastomosis by Billroth-I and stem vagotomy, manifestations of gastrostasis and diarrhea were stopped in the remote postoperative period. When assessing the quality of life, there were no unsatisfactory results, all previously operated patients led their usual lifestyle, maintained their working capacity, and did not require re-hospitalization.

Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...