Related Experiment Video
Updated: Oct 14, 2025

Three-dimensional Location Approach with Silk Thread Guided Laparoscopic Segmentectomy for Liver Tumor
Published on: May 23, 2025
Augmented reality in laparoscopic liver resection evaluated on an ex-vivo animal model with pseudo-tumours
Mourad Adballah1,2, Yamid Espinel1, Lilian Calvet1,3
1Institut Pascal, UMR6602, Endoscopy and Computer Vision Group, Faculté de Médecine, Bâtiment 3C, 28 place Henri Dunant, 63000, Clermont-Ferrand, France.

Background:
The aim of this study was to assess the performance of our augmented reality (AR) software (Hepataug) during laparoscopic resection of liver tumours and compare it to standard ultrasonography (US).
Materials And Methods:
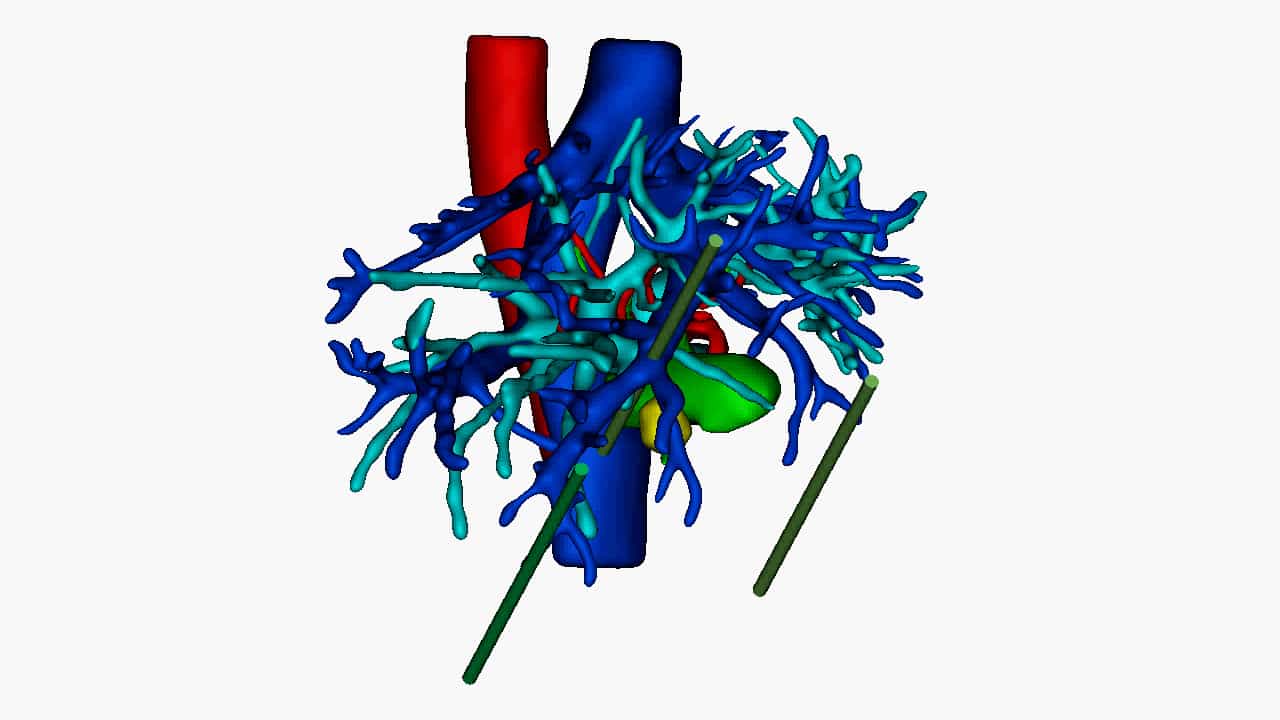
Ninety pseudo-tumours ranging from 10 to 20 mm were created in sheep cadaveric livers by injection of alginate. CT-scans were then performed and 3D models reconstructed using a medical image segmentation software (MITK). The livers were placed in a pelvi-trainer on an inclined plane, approximately perpendicular to the laparoscope. The aim was to obtain free resection margins, as close as possible to 1 cm. Laparoscopic resection was performed using US alone (n = 30, US group), AR alone (n = 30, AR group) and both US and AR (n = 30, ARUS group). R0 resection, maximal margins, minimal margins and mean margins were assessed after histopathologic examination, adjusted to the tumour depth and to a liver zone-wise difficulty level.
Results:
The minimal margins were not different between the three groups (8.8, 8.0 and 6.9 mm in the US, AR and ARUS groups, respectively). The maximal margins were larger in the US group compared to the AR and ARUS groups after adjustment on depth and zone difficulty (21 vs. 18 mm, p = 0.001 and 21 vs. 19.5 mm, p = 0.037, respectively). The mean margins, which reflect the variability of the measurements, were larger in the US group than in the ARUS group after adjustment on depth and zone difficulty (15.2 vs. 12.8 mm, p < 0.001). When considering only the most difficult zone (difficulty 3), there were more R1/R2 resections in the US group than in the AR + ARUS group (50% vs. 21%, p = 0.019).
Conclusion:
Laparoscopic liver resection using AR seems to provide more accurate resection margins with less variability than the gold standard US navigation, particularly in difficult to access liver zones with deep tumours.