Related Experiment Video
Updated: Jun 11, 2025
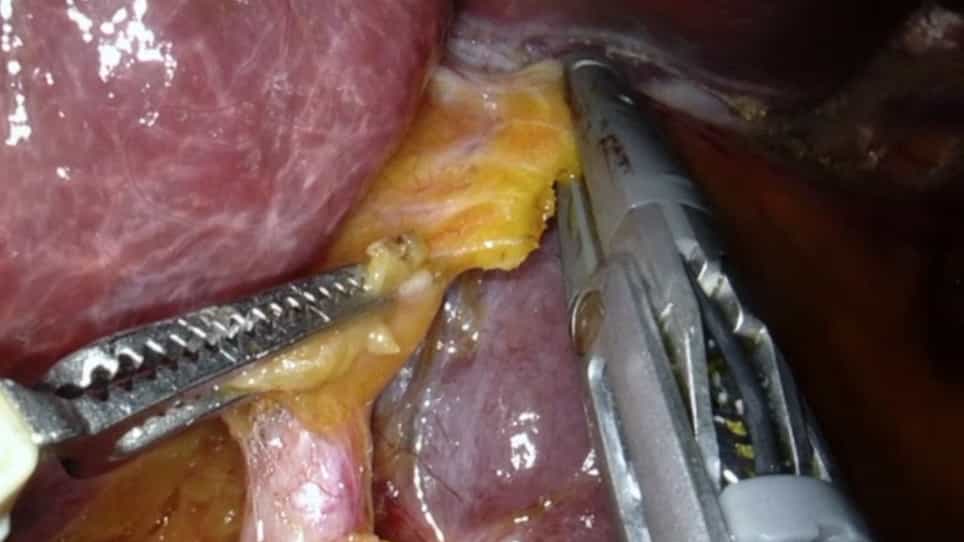

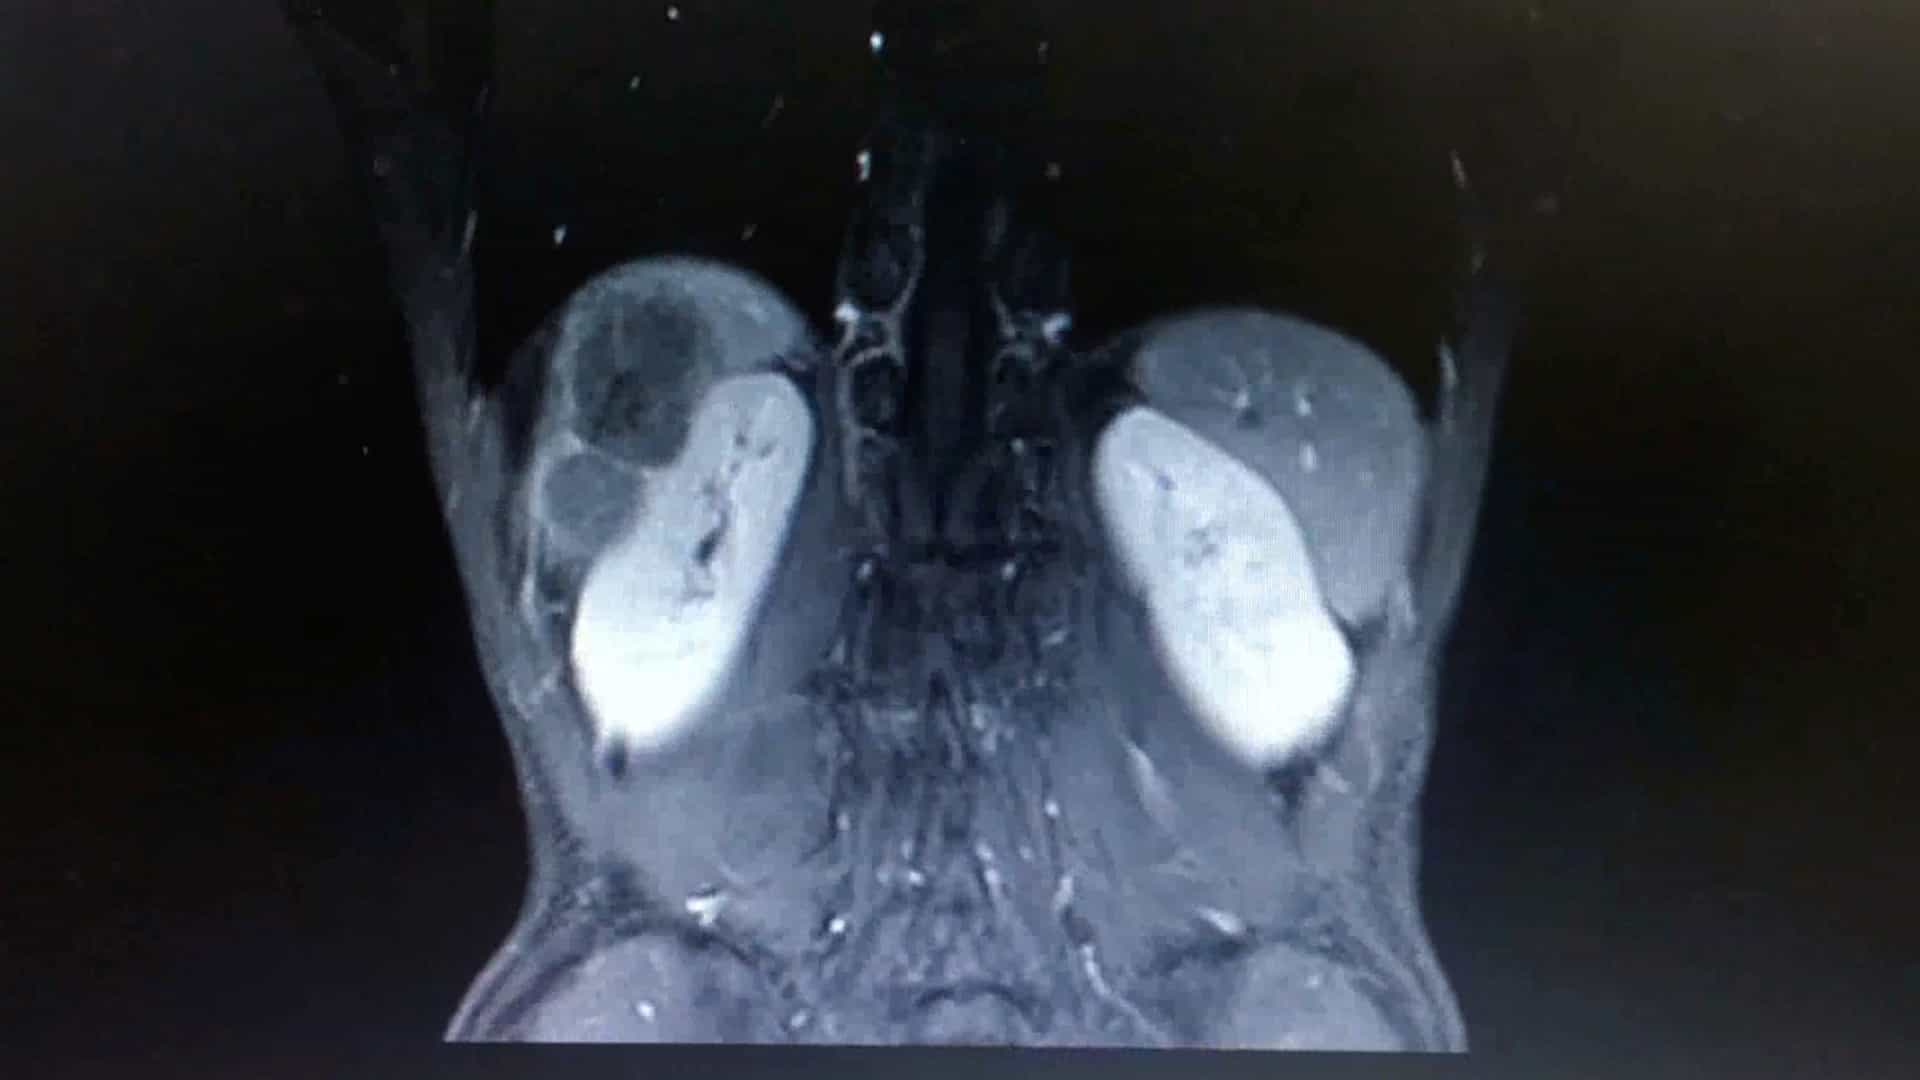
Robotic Left Hepatectomy using Indocyanine Green Fluorescence Imaging for an Intrahepatic Complex Biliary Cyst
Published on: June 24, 2022
Risk factors and outcomes of conversions in robotic and laparoscopic liver resections: A nationwide analysis
Gabriela Pilz da Cunha1, Jasper P Sijberden1, Paul Gobardhan2
1Department of Surgery, Amsterdam UMC, Location University of Amsterdam, Amsterdam, the Netherlands; Cancer Center Amsterdam, Amsterdam, the Netherlands; Department of Surgery, Fondazione Poliambulanza Istituto Ospedaliero, Brescia, Italy.

Background:
Unfavorable intraoperative findings or incidents during minimally invasive liver surgery may necessitate conversion to open surgery. This study aimed to identify predictors for conversion in minimally invasive liver surgery and gain insight into outcomes following conversions.
Methods:
This nationwide, retrospective cohort study compared converted and non-converted minimally invasive liver surgery procedures using data from 20 centers in the Dutch Hepatobiliary Audit (2014-2022). Propensity score matching was applied. Subgroup analyses of converted robotic liver resection versus laparoscopic liver resection and emergency versus non-emergency conversions were performed. Predictors for conversions were identified using backward stepwise multivariable logistic regression.
Results:
Of 3,530 patients undergoing minimally invasive liver surgery (792 robotic liver resection, 2,738 laparoscopic liver resection), 408 (11.6%) were converted (4.9% robotic liver resection, 13.5% laparoscopic liver resection). Conversion was associated with increased blood loss (580 mL [interquartile range 250-1,200] vs 200 mL [interquartile range 50-500], P < .001), major blood loss (≥500 mL, 58.8% vs 26.7%, P < .001), intensive care admission (19.0% vs 8.4%, P = .005), overall morbidity (38.9% vs 21.0%, P < .001), severe morbidity (17.9% vs 9.6%, P = .002), and a longer hospital stay (6 days [interquartile range 5-8] vs 4 days [interquartile range 2-5], P < .001) but not mortality (2.2% vs 1.2%, P = .387). Emergency conversions had increased intraoperative blood loss (1,500 mL [interquartile range 700-2,800] vs 525 mL [interquartile range 208-1,000], P < .001), major blood loss (87.5% vs 59.3%, P = .005), and intensive care admission (27.9% vs 10.6%, P = .029), compared with non-emergency conversions. Robotic liver resection was linked to lower conversion risk, whereas American Society of Anesthesiologists grade ≥3, larger lesion size, concurrent ablation, technically major, and anatomically major resections were risk factors.
Conclusion:
Both emergency and non-emergency conversions negatively impact perioperative outcomes in minimally invasive liver surgery. Robotic liver resection reduces conversion risk compared to laparoscopic liver resection.