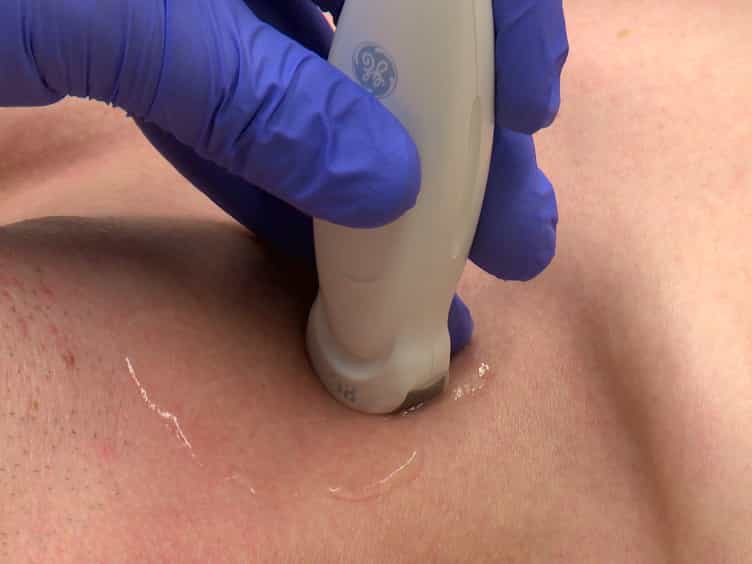
Ultrasound-guided axillary access outperforms subclavian puncture for cardiac implantable electronic device implantation: A network meta-analysis of 130,831 patients
Related Experiment Video
Updated: Aug 6, 2026
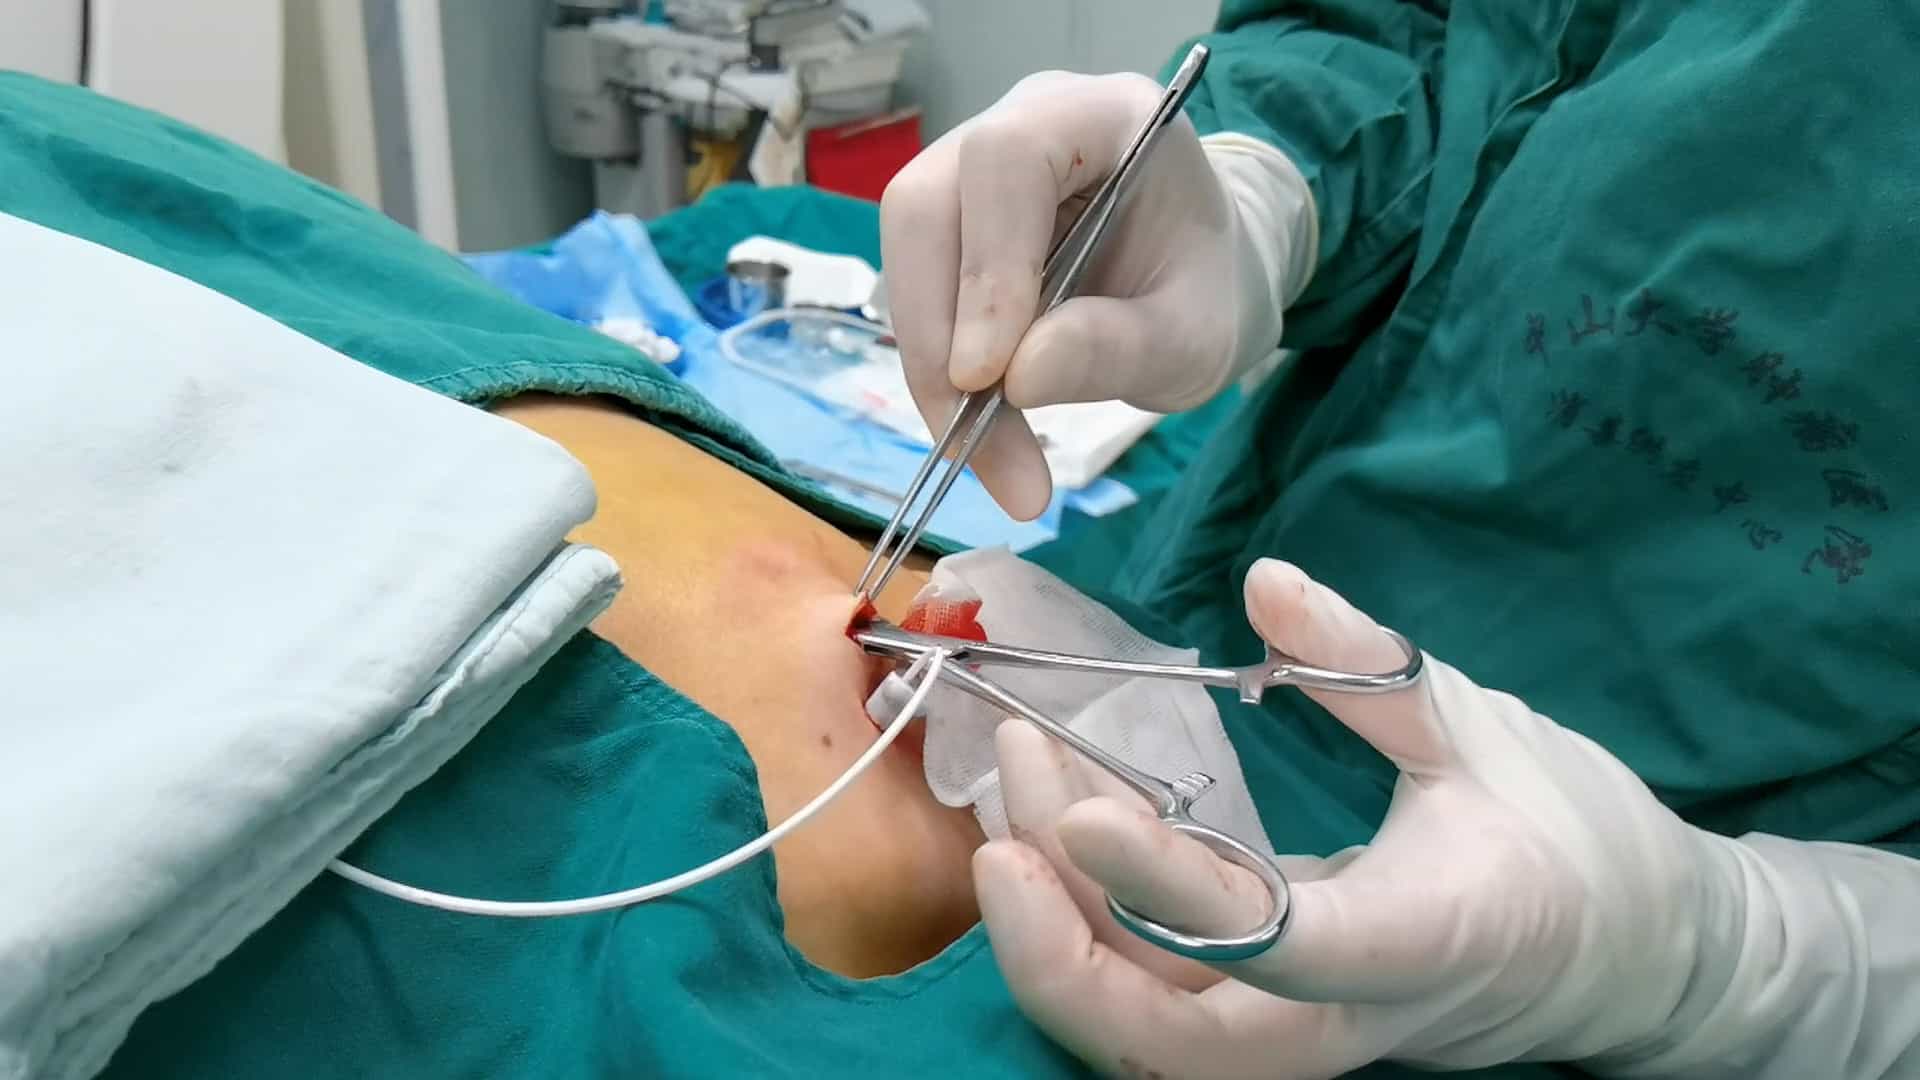
Computed Tomography (CT) Guided Implantation of a Totally Implantable Venous Access Port (TIVAP) through Subclavian Vein
Published on: January 13, 2026
Maria Eduarda Marquez Almeida1, Isabella Rodrigues Ribeiro1, Charles Karel Martins1
1Medical Department, School of Medical and Life Sciences, Pontifical Catholic University of Goiás, Goiânia, Goiás, Brazil.

Background:
The optimal venous access route for cardiac implantable electronic device implantation remains debated.
Objective:
We compared the efficacy and safety of subclavian vein puncture (SVP), cephalic vein cutdown (CVP), and axillary vein puncture guided by fluoroscopy (FL-AVP) and ultrasound (US-AVP).
Methods:
A systematic search of PubMed, Embase, Cochrane Central, and Web of Science (until September 24, 2025) identified randomized and observational studies comparing ≥2 venous access techniques for cardiac implantable electronic device implantation in adults. A frequentist random-effects network meta-analysis estimated odds ratios (ORs) or standardized mean differences with 95% confidence intervals. Heterogeneity, network consistency, and ranking probabilities were assessed using P scores.
Results:
Of the 4316 records screened, 25 studies (130,831 patients) were included. CVP was significantly less successful than FL-AVP (OR 0.18), SVP (OR 0.14), and US-AVP (OR 0.17). SVP carried a higher risk of overall complications than US-AVP (OR 2.21). Procedure time was longer for CVP than for FL-AVP or US-AVP. FL-AVP entailed greater fluoroscopy time and radiation exposure than US-AVP. Pneumothorax occurred less frequently with CVP and FL-AVP than with SVP, whereas lead dislodgement and pericardial effusion were less common with CVP than with SVP. Network ranking favored SVP for procedural success and US-AVP for safety and radiation reduction.
Conclusion:
Axillary (ultrasound- or fluoroscopy-guided) and cephalic approaches outperform subclavian puncture in risk-benefit. US-AVP is considered the first-line technique, FL-AVP is a valid alternative when ultrasound is unavailable, and CVP is preferred for selected anatomies. In contrast, SVP should be reserved for bailout cases.PROSPERO CRD420251017329.