Related Experiment Video
Updated: Oct 3, 2026
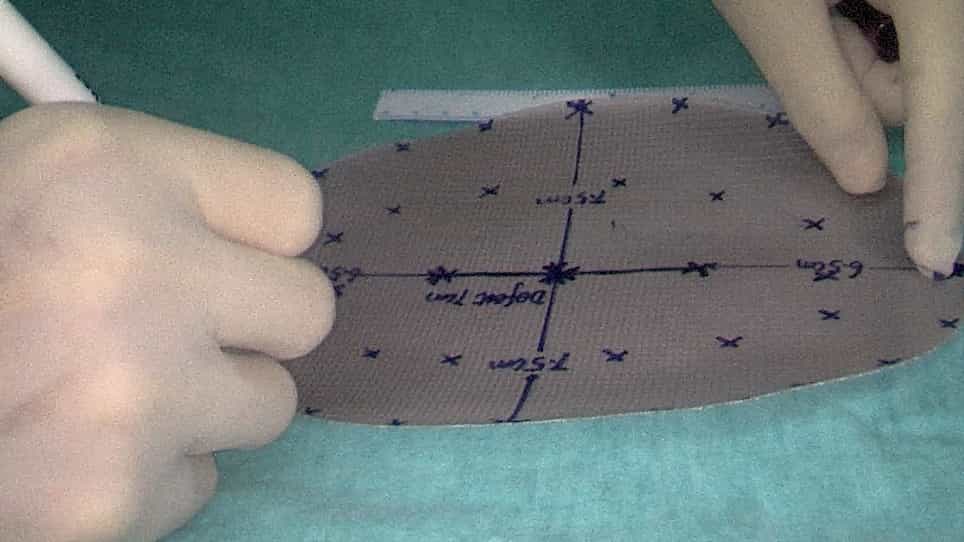
Application of a New Mesh Fixation Method in Laparoscopic Incisional Hernia Repair
Published on: December 23, 2022
Self-gripping mesh without fixation versus anatomical mesh with tack fixation for laparoscopic TAPP inguinal hernia
Guvenc Diner1, Guven Erdogrul2, Boran Cihat Karakus2
1Deparment of General Surgery, Mersi̇n Sehir Research and Training Hospital, Mersin, Türkiye. guvencdiner@yahoo.com.

Background:
Mesh characteristics and fixation techniques may influence operative efficiency, postoperative pain, and resource utilization during laparoscopic trans-abdominal preperitoneal (TAPP) inguinal hernia repair. However, comparisons between self-gripping and anatomically contoured meshes may be inherently confounded when a self-gripping mesh is used without mechanical fixation, whereas an anatomical mesh is routinely fixed. We therefore compared these two routinely used mesh-fixation strategies in patients undergoing primary unilateral TAPP repair.
Methods:
We retrospectively reviewed 346 patients who underwent primary unilateral conventional laparoscopic TAPP repair between January 2022 and December 2025. Patients were treated using either a self-gripping mesh without additional mechanical fixation (n = 157) or an anatomically contoured mesh secured with absorbable tack fixation (n = 189). The primary outcome was skin-to-skin operative duration. Secondary outcomes included postoperative pain at 6 and 24 h, hospital length of stay, postoperative complications, 12-month recurrence, and direct material costs. Multi-variable linear regression was performed to identify factors independently associated with operative duration. Given the low number of observed complications, an exploratory multi-variable logistic regression analysis was performed and interpreted cautiously.
Results:
Mean operative duration was significantly shorter in the self-gripping group than in the anatomical mesh with tack fixation group (52.7 ± 15.9 vs. 61.7 ± 19.2 min, respectively; p < 0.001). Postoperative VAS scores were lower in the self-gripping group at both 6 h (5.0 ± 1.2 vs. 6.1 ± 1.4; p < 0.001) and 24 h (5.6 ± 1.3 vs. 6.7 ± 1.5; p < 0.001). Mean hospital length of stay was 1.2 ± 0.4 versus 1.4 ± 0.5 days (p < 0.001), although the absolute difference was modest. Total direct material costs were significantly lower with the self-gripping strategy ($141.2 ± 5.1 vs. $192.2 ± 12.2; p < 0.001), primarily because no disposable fixation device was required. Postoperative complications were uncommon and did not differ significantly between groups (1.9% vs. 3.2%; p = 0.509). At 12 months, one recurrence occurred in the anatomical mesh group and none in the self-gripping group (0.0% vs. 0.5%; p = 1.000).
Conclusions:
In this retrospective cohort, the self-gripping mesh/no-fixation strategy was associated with shorter operative duration, lower early postoperative pain scores, and lower direct material costs than the anatomical mesh/tack-fixation strategy. These findings should be interpreted as differences between two combined mesh-fixation strategies rather than as evidence that one mesh design is intrinsically superior to the other. Larger prospective comparative studies are needed to determine the independent contributions of mesh design and fixation technique.