Related Experiment Video
Updated: Feb 6, 2026

Insulin Injection and Hemolymph Extraction to Measure Insulin Sensitivity in Adult Drosophila melanogaster
Published on: June 30, 2011
Paediatric insulin injection technique: The softer side
Sanjay Kalra1, Asma Al Deeb2, Mudita Dhingra3
1Department of Endocrinology, Bharti Hospital, Karnal, India.

Insights
This study details best practices for pediatric insulin injections, considering children's unique needs for a positive diabetes management experience. It emphasizes tailoring techniques for a healthier, happier injection process for young patients.
Area of Science:
- Pediatric Endocrinology
- Diabetes Management
- Patient Education
Background:
- Insulin therapy is crucial for managing pediatric diabetes.
- Standard injection techniques may not fully address the unique needs of children and adolescents.
- A positive injection experience is vital for adherence and long-term health outcomes.
Purpose of the Study:
- To highlight unique aspects of insulin injection technique in the pediatric population.
- To correlate child-specific characteristics with optimal injection practices.
- To promote a positive and healthy insulin injection experience for children and adolescents with diabetes.
Main Methods:
- Review of anatomical, neurodevelopmental, and psychosocial characteristics of pediatric age groups.
- Correlation of these characteristics with established insulin delivery guidelines.
- Identification of 'best practices' for pediatric insulin injection technique.
Main Results:
- Paediatric insulin injection technique requires consideration of age-specific anatomical, developmental, and psychosocial factors.
- Tailored approaches can lead to improved injection experiences for children.
- The 'softer side' of technique complements existing technical guidelines.
Conclusions:
- Optimizing insulin injection technique in children necessitates a holistic approach, integrating developmental and psychosocial considerations.
- Further research is encouraged to address the specific challenges faced by young people with diabetes.
- Implementing these best practices can enhance the overall well-being and diabetes management of pediatric patients.
Abstract:
This communication highlights the unique features of insulin injection technique in the paediatric age group. It describes the anatomical, neurodevelopmental and psychosocial characteristics of children and adolescents of various age groups. These are correlated to highlight 'best practices' or 'injection manner' which diabetes care providers and care givers should observe, in order to achieve a 'happy' and healthy insulin injection experience for the child. The softer side of paediatric insulin injection technique adds to existing guidelines on insulin delivery. It encourages research on the special needs and challenges of children and adolescents living with diabetes.
Related Concept Videos
 01:05
Insulin Secretory Vesicles
 01:28
Insulin: The Receptor and Signaling Pathways
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into...
 01:25
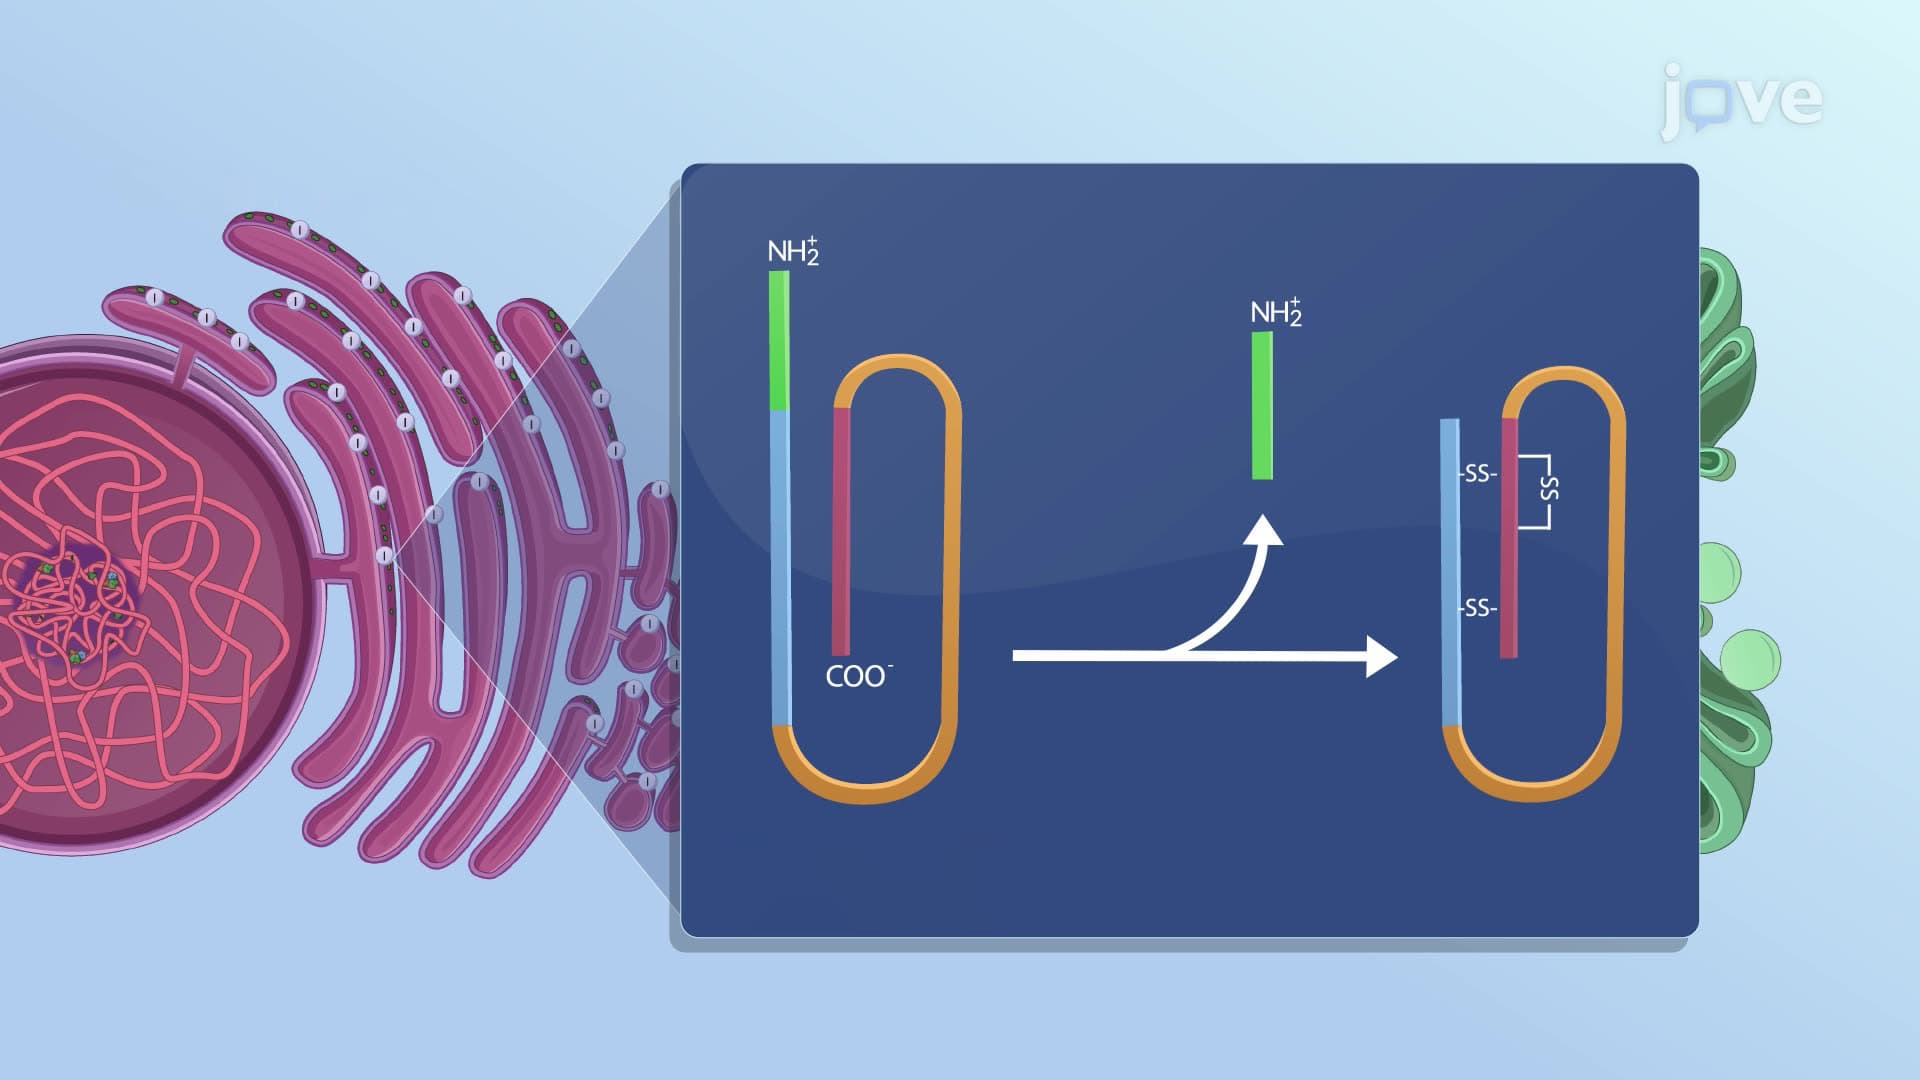
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are...