Related Experiment Video
Updated: Sep 21, 2025
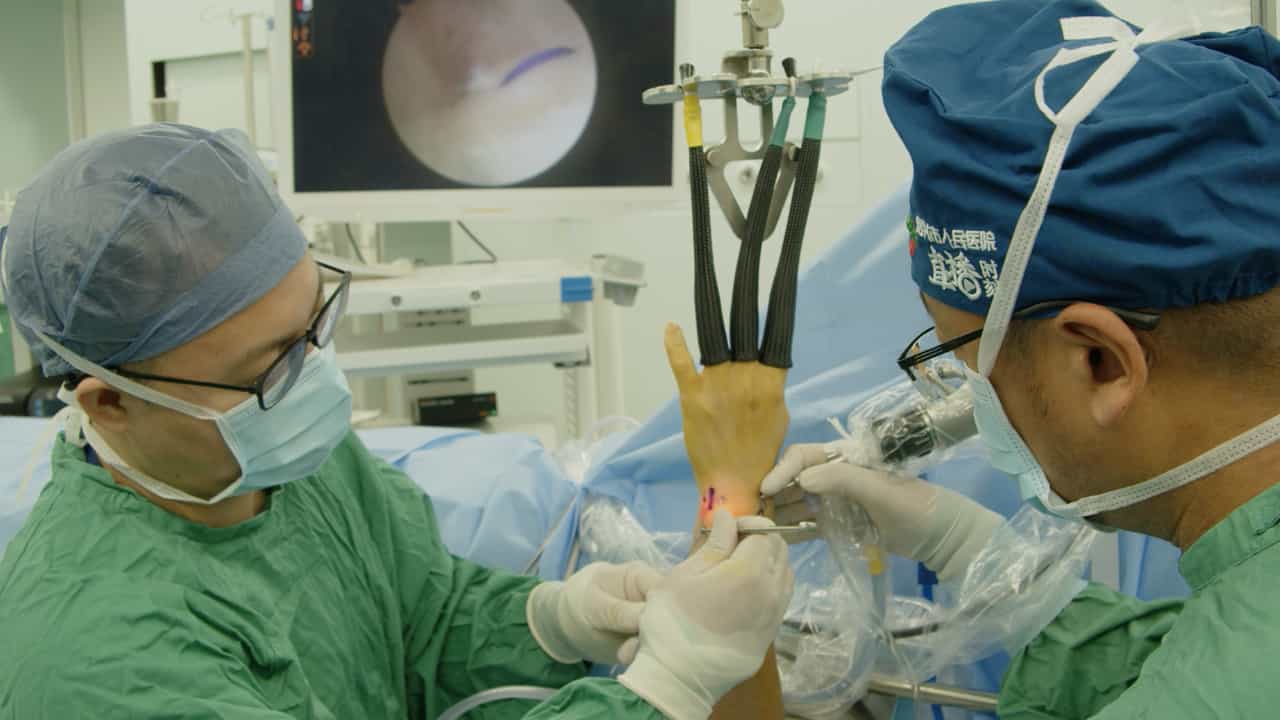

Novel Triple-Loop Technique for Suturing TFCC Injuries without Transosseous Tunnel
Published on: May 23, 2025
Optimal Lateral Ulnar Collateral Ligament Repair Site After Placement of the Internal Joint Stabilizer

Background:
The optimal location to repair the lateral ulnar collateral ligament (LUCL) following placement of the internal joint stabilizer (IJS) has not been defined. The placement of the IJS occupies the ideal native repair site, the isometric point on the lateral epicondyle, necessitating non-anatomic repair of the LUCL. This may lead to a loss of flexion, extension, or both. We present a cadaveric study aimed to determine the ideal non-anatomic repair location that maximizes postoperative range of motion.
Methods:
Range of motion of 10 cadaveric elbows were tested with the lateral ulnar collateral ligament complex intact. The ligament was then elevated from the capitellum and the IJS device was implanted. Five lateral collateral repair positions were tested using quadrants to classify the repair positions. The ligament was repaired using suture in a Krakow fashion placed through drill holes in the lateral capitellum, then secured against the posterior cortex. Elbow range of motion was documented for both flexion and ex- tension in all repair positions for each of the 10 cadaveric specimens. Statistical analysis was performed using an analysis of variance (ANOVA) and a Tukey-Kramer post hoc analysis to determine statistical significance.
Results:
There was a statistically significant difference between elbow range of motion in each repair position and the native elbow in all but position 3, which was anterior and distal to the central IJS axis pin (8° loss of flexion and 6° loss of extension). Flexion was significantly different in only position 2 (15° loss), while extension was different in both position 1 (51° loss) and position 4 (42° loss). Total motion loss was significant for positions 1 (57°), 2 (16°), 4 (48°), and 5 (24°).
Conclusions:
When using an IJS elbow stabilizing device, since the axis pin occupies the anatomic origin of the lat- eral ulnar collateral ligament, the repair should be placed as close as possible to the isometric point in the anterior and distal quadrant of the lateral capitellum to maximize postoperative elbow range of motion.

